
The diagnosis and named anatomic target come before the procedure.
Peripheral nerve procedures
Suprascapular Radiofrequency Treatment
Suprascapular radiofrequency treatment applies controlled energy near a selected shoulder sensory pathway. Evidence is mixed and low certainty, so diagnosis, target selection, alternatives, and functional goals must be explicit.
Quick orientation
What to know first
A nerve block, radiofrequency procedure, joint injection, and neuromodulation have different purposes.
Response to one step can inform the plan but does not prove diagnosis or require a next procedure.
Target and mechanism
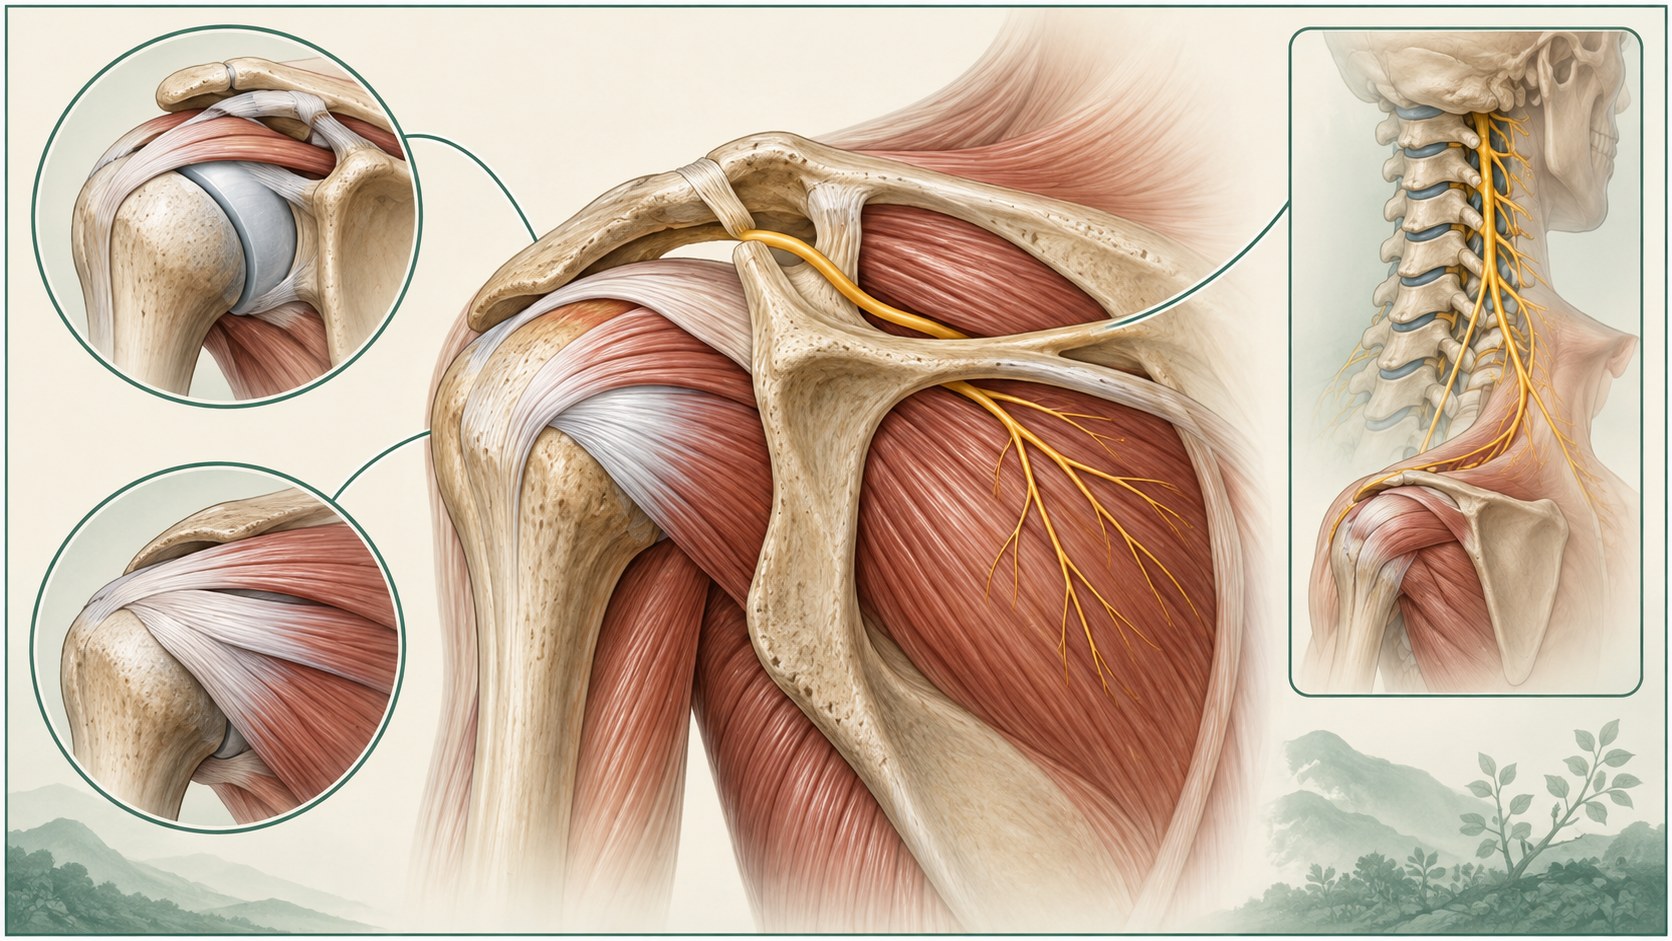
What suprascapular radiofrequency treatment targets
The suprascapular nerve carries sensory input from parts of the shoulder and motor supply to important muscles. Target location and technique matter because shoulder innervation is broader than one nerve.
Related care
Conditions this treatment may be considered for
These related options are educational. They do not establish a diagnosis, candidacy, recommendation, or required treatment sequence.
Treatment Sequence
Shoulder Osteoarthritis
Later therapeutic step only after target-specific assessment and appropriate response.
Explore this pageTreatment Sequence
Shoulder Pain
For selected persistent shoulder pain after a supportive block; evidence is limited, and pulsed and thermal techniques differ
Explore this pagePatient selection
Questions that decide whether suprascapular radiofrequency treatment fits
Selection begins with a clinically coherent diagnosis and a specific anatomic target. It also considers competing diagnoses, prior treatment, medication and bleeding risk, infection risk, goals, and whether a procedure is the right next decision.
A clinically coherent diagnosis and named target
Meaningful functional limitation despite appropriate initial care or a focused diagnostic question
A risk review that supports the proposed procedure
A defined goal and reassessment plan
Evidence at a glance
Evidence at a glance
Study results depend on diagnosis, selection, comparator, technique, outcome, and follow-up.
A 2021 meta-analysis found no benefit over conventional care in randomized pulsed-radiofrequency trials and low-quality evidence for ablative techniques.
A 2024 review found possible improvement but emphasized high risk of bias, heterogeneity, and low certainty.
Evidence from one shoulder diagnosis or technique should not be generalized to all shoulder pain.
Decision process
Steps before suprascapular radiofrequency treatment
A procedure is an optional treatment discussion, not an automatic step. The response must be reassessed against the usual symptoms and meaningful activities. A limited, absent, or discordant response should reopen the diagnosis and alternatives instead of triggering an automatic series.
Confirm the diagnosis and named target
Review alternatives, evidence quality, and medical risks
Define meaningful functional and symptom goals
Reassess the result before deciding what comes next
A staged decision
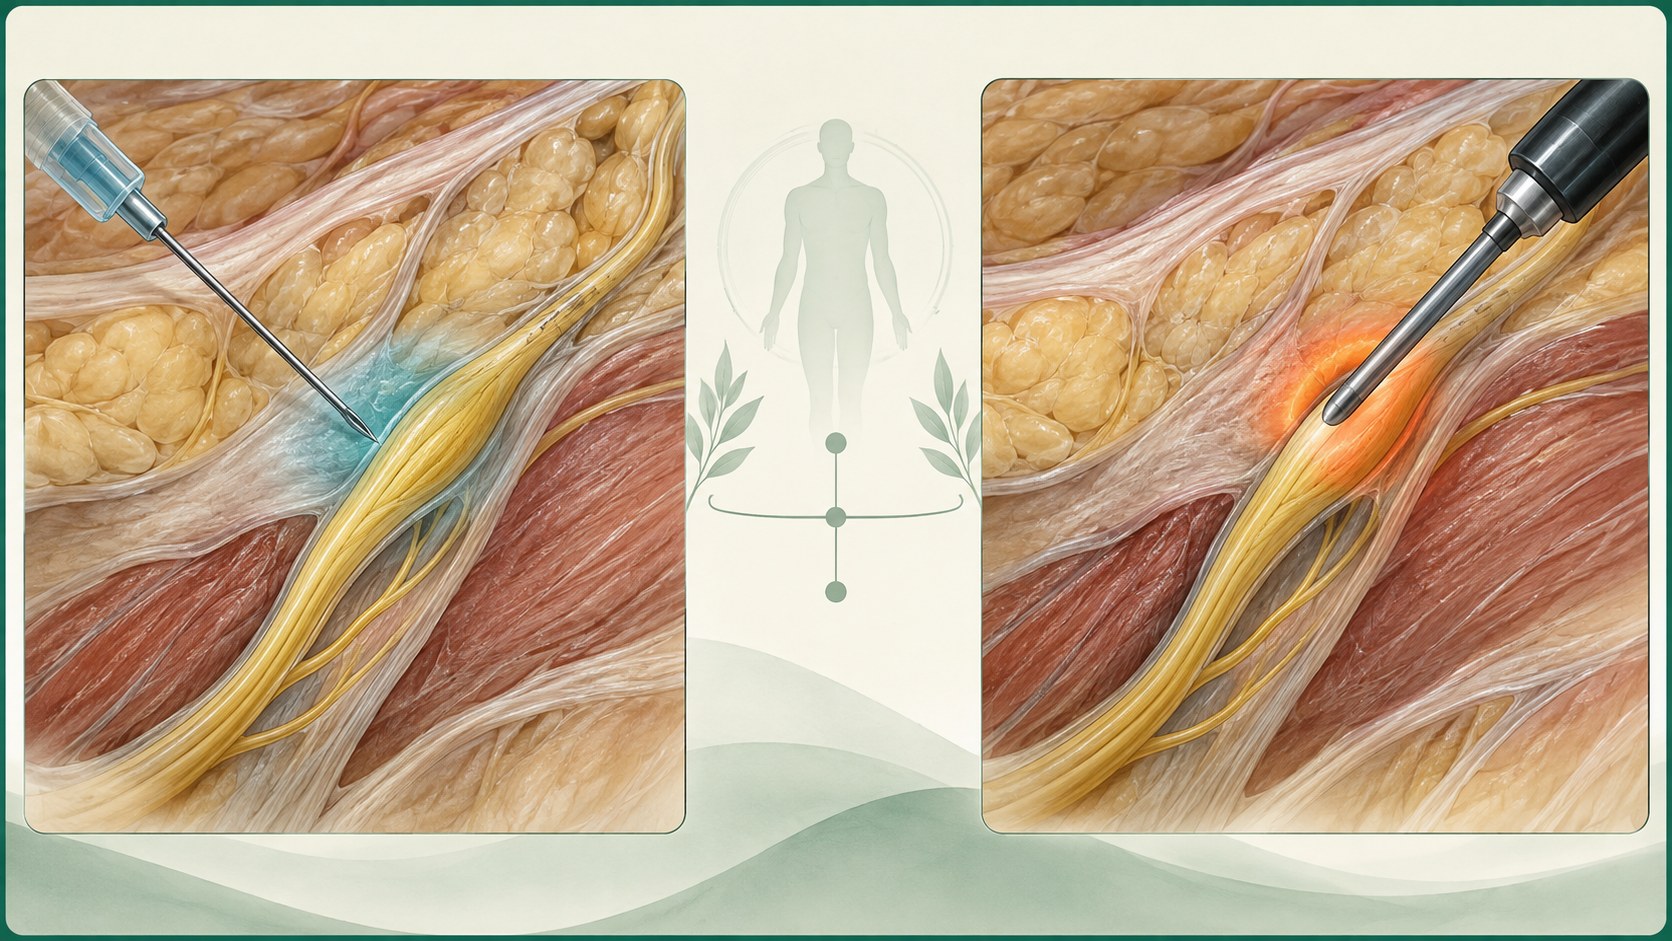
How suprascapular radiofrequency treatment works
Image guidance is used to position the radiofrequency cannula near the selected target after diagnosis and selection review. Pulsed and ablative techniques are not interchangeable, and technical settings are individualized.
Decision quality matters
Evidence, limits, and who it may fit
A listed option or imaging finding does not establish candidacy. Evidence and uncertainty must be matched to the individual question.
Risks and limits
Suprascapular radiofrequency treatment risks and limits
A 2021 meta-analysis found no benefit over conventional care in randomized pulsed-radiofrequency trials and low-quality evidence for ablative techniques. A 2024 review found possible improvement but emphasized high risk of bias, heterogeneity, and low certainty. Evidence from one shoulder diagnosis or technique should not be generalized to all shoulder pain.
Bleeding, infection, temporary numbness or weakness, nerve injury, local anesthetic toxicity, allergic or medication effects, and target-specific injury require individualized consent.
Medication, volume, radiofrequency settings, sedation, medication holds, driving, activity, and follow-up are not universal protocols.
A procedure does not replace evaluation of progressive neurologic loss, urgent disease, or a surgical problem.
The visit
Your consultation for suprascapular radiofrequency treatment
The visit should define the diagnosis, intended target, evidence, alternatives, risks, and the next useful decision. Medication, frequency, sedation, medication holds, driving, and aftercare remain individualized clinician decisions.
Common questions
Suprascapular Radiofrequency Treatment FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is this proven for every shoulder diagnosis?
No. Studies combine different diagnoses and techniques, limiting certainty.
Must RFA follow a helpful block?
No. A block may inform selection, but progression is not automatic and benefit is not guaranteed.
Can RFA weaken the shoulder?
The suprascapular nerve has motor functions, so target choice and consent must address nerve-specific risks.
Question before procedure
Ask about suprascapular radiofrequency treatment in Allen, TX
A consultation can clarify whether a selected procedure, another treatment, continued conservative care, or referral fits the clinical picture.
