
Symptoms, examination, function, and imaging must be interpreted together.
Joint and musculoskeletal conditions
Shoulder Osteoarthritis
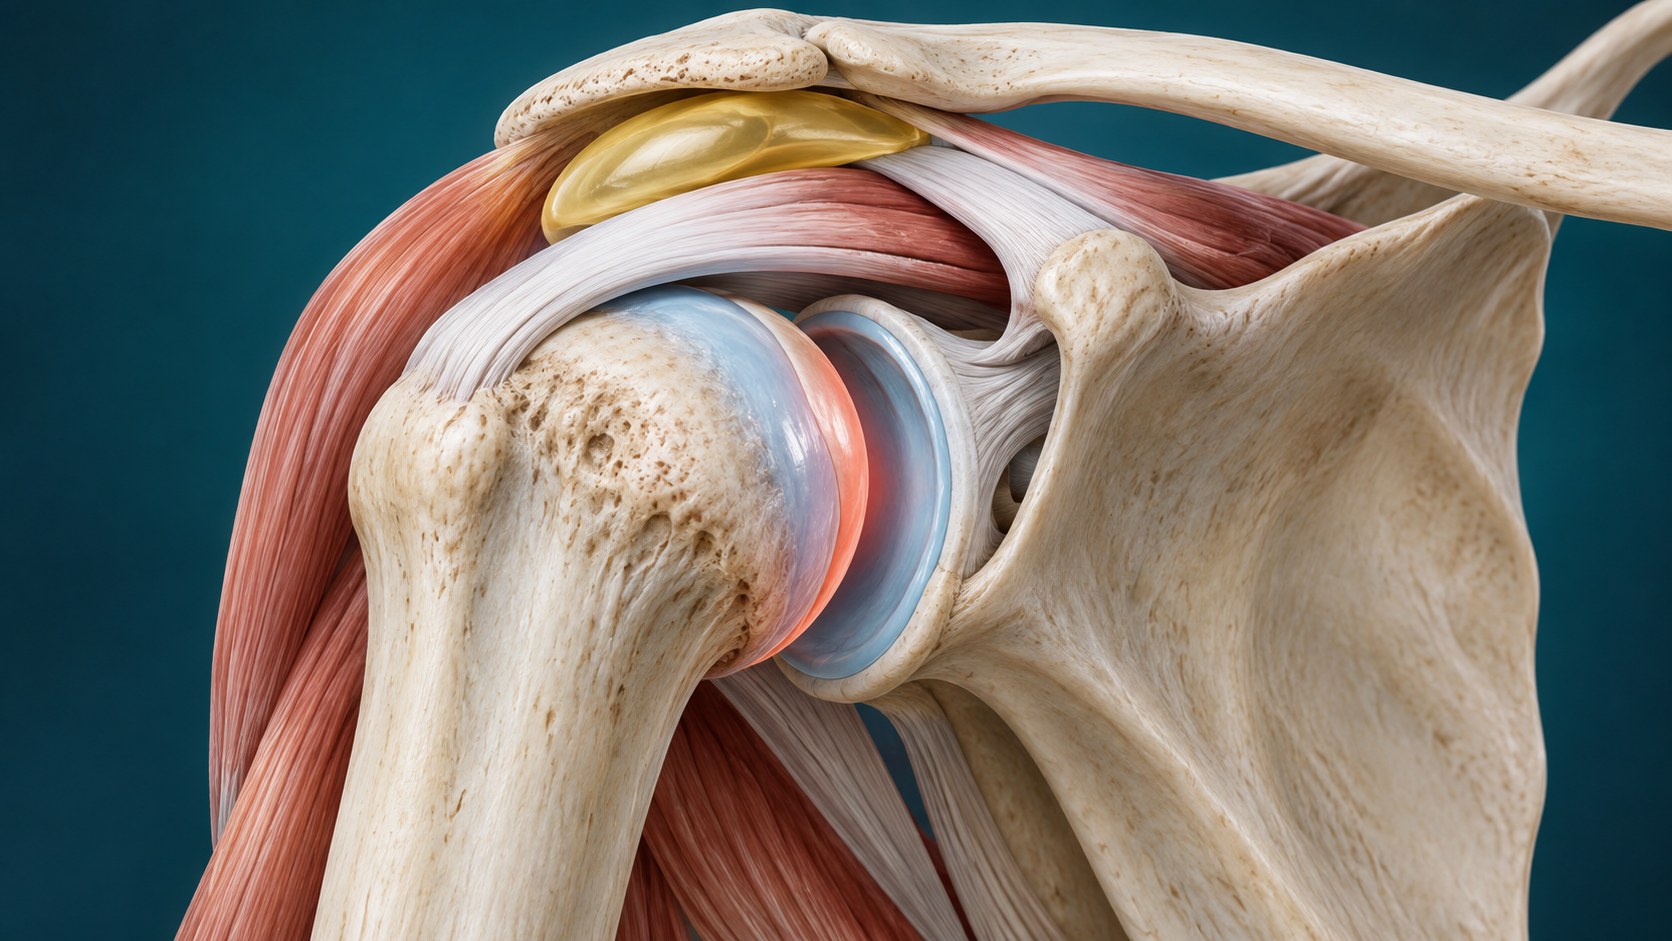
Shoulder osteoarthritis affects the ball-and-socket glenohumeral joint and may cause deep pain, stiffness, and loss of motion. Many other shoulder and neck disorders can produce similar symptoms.
Quick orientation
What to know first
Neighboring joints, tendons, nerves, and referred pain can overlap.
A procedure is one possible tool, not proof of the diagnosis or an automatic next step.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
Suprascapular Nerve Block
May serve as a target-specific assessment before a later nerve procedure in selected chronic shoulder pain.
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
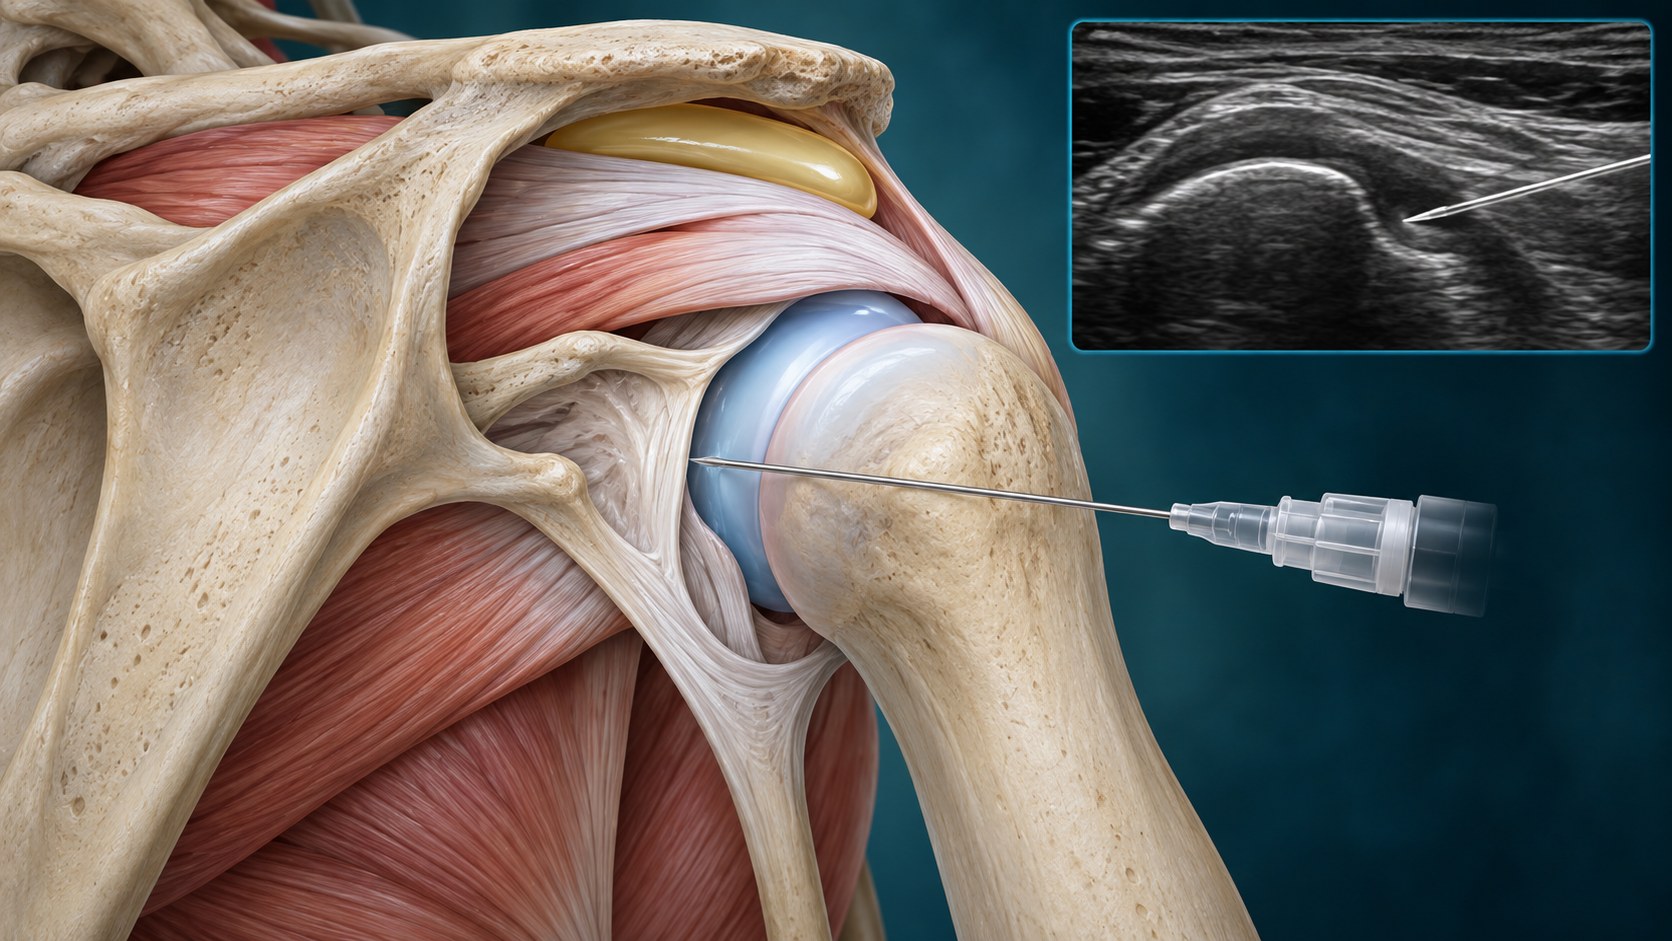
Shoulder Joint Injection
May be considered for selected joint-mediated shoulder pain after diagnosis and treatment-goal review.
May come later
A later procedure is considered only when evaluation and the response to earlier steps support it.
Later treatment option
Suprascapular Radiofrequency Treatment
Later therapeutic step only after target-specific assessment and appropriate response.
Symptoms are clues, not a diagnosis
What shoulder osteoarthritis can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Pain location and movement sensitivity can narrow the differential but rarely identify one structure alone.
Stiffness, range of motion, loading tolerance, weakness, swelling, and daily function add diagnostic context.
The pattern should be checked for referred pain, neurologic features, inflammatory disease, injury, and other alternatives.
Relevant anatomy
What causes shoulder osteoarthritis
The humeral head moves against the glenoid surface. Cartilage loss and bony change may limit motion, but the rotator cuff, bursa, acromioclavicular joint, and cervical nerves remain separate possible sources of shoulder-region symptoms.
History and examination first
How shoulder osteoarthritis is diagnosed
Evaluation combines the history, movement and loading pattern, focused examination, functional goals, and selective imaging. Structural change can support a diagnosis, but imaging severity and symptom severity may not match.
Keep the differential open
Conditions that can feel like shoulder osteoarthritis
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Referred spinal or nerve-related pain
Tendon, bursa, muscle, or neighboring joint disorders
Inflammatory arthritis, infection, fracture, or another less common cause when the history suggests it
Core care
Non-surgical care for shoulder osteoarthritis
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education, pacing, and movement matched to irritability
Progressive strength, mobility, and function when appropriate
Medication review that accounts for individual risks
Reassessment when the pattern changes or improvement stalls
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
The AAOS guideline highlights important limitations in evidence for many nonsurgical glenohumeral osteoarthritis treatments.
Physical therapy may help selected patients, while the exact program must match irritability and goals.
Hyaluronic acid has not shown benefit for glenohumeral osteoarthritis in the AAOS evidence review.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When shoulder osteoarthritis needs urgent care
These findings can change the timing or destination of care.
Fever, a hot swollen joint, or systemic illness
Major trauma or inability to bear weight or use the limb
Rapidly progressive weakness, numbness, or a new emergency symptom pattern
The visit
Your first visit for shoulder osteoarthritis
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the symptom pattern and meaningful functional limits
Examine the joint and neighboring regions before attributing symptoms to one structure
Review imaging only in clinical context
Choose among rehabilitation, medication review, a selected procedure discussion, or referral without assuming a fixed sequence
Common questions
Shoulder Osteoarthritis FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is shoulder arthritis the same as a rotator cuff problem?
No. They can coexist, but they involve different structures and may need different plans.
Can imaging identify the whole cause of shoulder pain?
No. Imaging supports the evaluation but must match the history, motion pattern, strength, and examination.
Does every arthritic shoulder need an injection or replacement?
No. Decisions depend on symptoms, function, response to conservative care, anatomy, goals, and risk.
Diagnosis before procedure
See a pain specialist for shoulder osteoarthritis in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
