
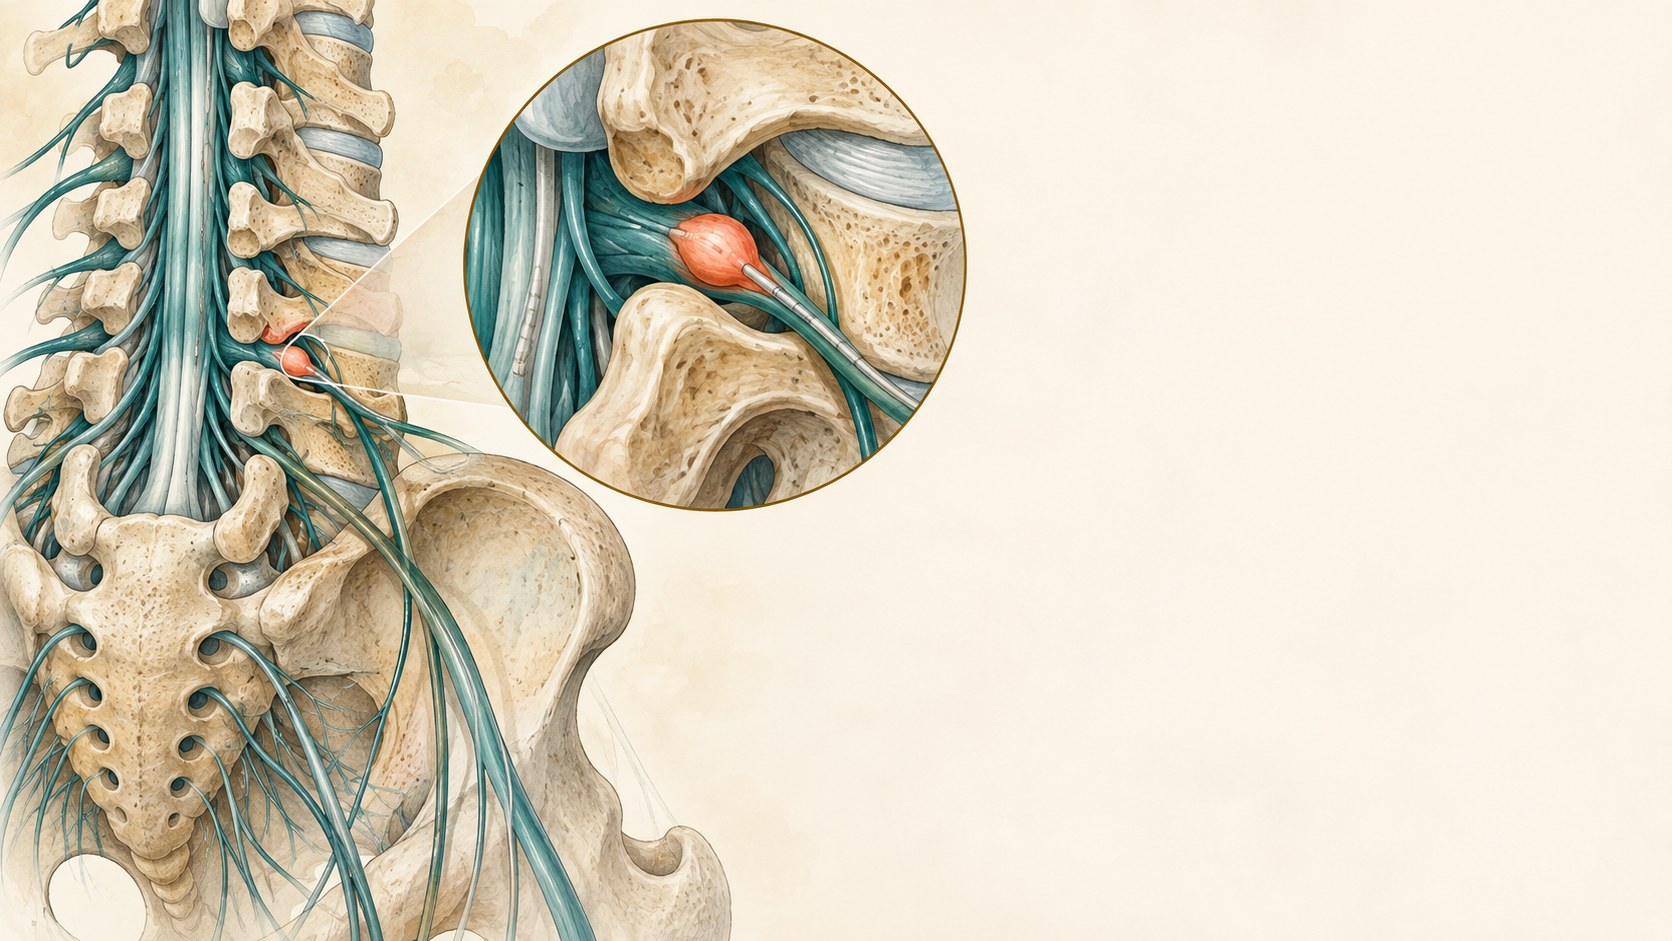
The target is a selected sensory ganglion near a spinal nerve root.
Neuromodulation
Dorsal Root Ganglion Stimulation
Dorsal root ganglion stimulation places leads near selected sensory ganglia to target a more focal pain distribution. Its strongest comparative evidence and US indication center on lower-limb CRPS and causalgia.
Quick orientation
What to know first
DRG can be useful when pain is focal and difficult to cover with broader stimulation.
Persistent pain after spine surgery may be considered only after an individualized evaluation; it is not presented as a primary indication here.
Target and mechanism
What DRG stimulation targets
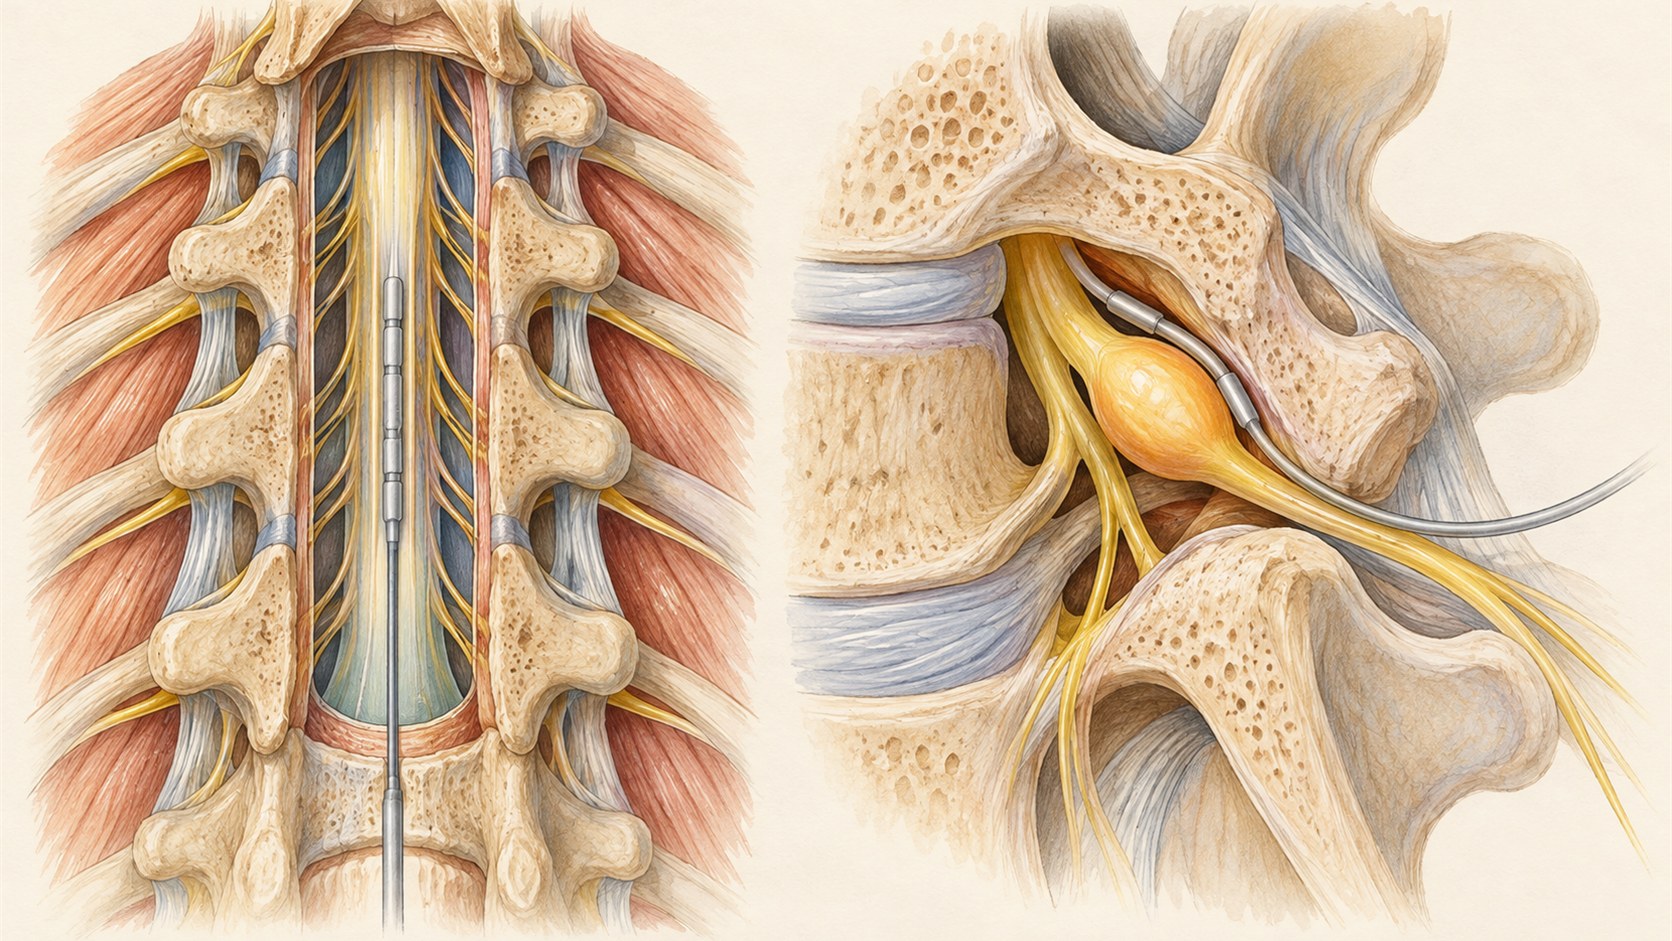
A dorsal root ganglion contains sensory nerve-cell bodies near the neural foramen. DRG leads are positioned near one or more selected ganglia, which differs anatomically and technically from placing SCS leads over the dorsal columns.
Learn what may come next
Related guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Care overview
Neuromodulation
Compare approved neuromodulation pathways and understand how modality selection differs by diagnosis, anatomy, and goals.
Open this guideSpecific treatment
Spinal Cord Stimulation
Understand spinal cord stimulation evaluation, trial, implantation, limitations, and selection context.
Open this guideSpecific treatment
Peripheral Nerve Stimulation
Understand peripheral nerve stimulation for selected named peripheral-nerve pain presentations.
Open this guideSpecific treatment
Vagus / Auricular Neuromodulation
Understand the actual nontraditional vagus/auricular neuromodulation service offered by the practice without implying implanted cervical VNS for epilepsy.
Open this guideRelated care
Conditions this treatment may be considered for
These related guides show educational connections. They do not establish candidacy, a recommendation, or a required sequence.
Alternative
Persistent Post-Surgical Spine Pain
Potential alternative for selected focal neuropathic presentations after reassessment.
Explore this pageTherapeutic Consideration
Complex Regional Pain Syndrome
May be considered for selected focal CRPS presentations within a trial-based pathway.
Explore this pagePatient selection
Questions that decide whether DRG stimulation fits
These questions help determine whether the proposed neural target and treatment plan fit the individual problem.
A documented focal lower-limb neuropathic pain pattern
CRPS or causalgia evaluated against accepted diagnostic criteria
Failure or intolerance of appropriate less-invasive care
Ability to complete a trial and long-term device follow-up
Evidence at a glance
Evidence at a glance
Evidence must be matched to the exact diagnosis, comparator, follow-up period, and system studied.
The ACCURATE randomized trial found higher treatment success with DRG stimulation than conventional SCS in selected lower-limb CRPS and causalgia.
The FDA indication is specific and should not be expanded by implication.
Evidence for persistent post-surgical spine pain remains limited and is not promoted as a featured relationship.
Decision process
Steps before DRG stimulation
The safest sequence starts with diagnosis and target, then compares alternatives and evidence, and only then considers a trial, temporary treatment, or implant.
Map the pain distribution and confirm the diagnosis
Choose target levels based on anatomy rather than a generic protocol
Define trial goals and review the result before implant
A staged decision
How DRG stimulation works
The pathway includes diagnostic review, selection of the ganglion level that matches the painful territory, medical and psychosocial risk assessment, a temporary trial, and a separate decision about permanent implantation.
Decision quality matters
Evidence, limits, and who it may fit
Relationship membership does not establish candidacy. Published results must be qualified by selection criteria, study design, durability, complications, and alternatives.
Risks and limits
DRG stimulation risks and limits
The ACCURATE randomized trial found higher treatment success with DRG stimulation than conventional SCS in selected lower-limb CRPS and causalgia. The FDA indication is specific and should not be expanded by implication. Evidence for persistent post-surgical spine pain remains limited and is not promoted as a featured relationship.
Infection, lead migration or fracture, neural injury, revision, and explant are material risks.
Focal targeting does not prove the diagnosis.
Evidence outside the approved and well-studied populations is less certain.
The visit
Your consultation for DRG stimulation
The visit should identify the diagnosis, the proposed neural target, the evidence that applies to that exact condition, alternatives, and a measurable next step.
Common questions
Dorsal Root Ganglion Stimulation FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
How is DRG stimulation different from SCS?
DRG stimulation targets a selected sensory ganglion near a spinal nerve root. SCS typically targets broader pathways near the spinal cord.
What conditions have the strongest evidence?
The strongest comparative evidence and US indication are for selected lower-limb CRPS and causalgia.
Is DRG automatically better for focal pain?
No. Focal distribution is one selection factor. Diagnosis, anatomy, prior care, risks, and the evidence for the specific indication still matter.
Target before technology
Ask about DRG stimulation in Allen, TX
A consultation can clarify whether this modality, another treatment, or continued diagnostic work is the appropriate next step.
