
Persistent pain can come from several structures or mechanisms.
Back & Spine
Persistent Post-Surgical Spine Pain
Pain that persists or returns after spine surgery is not one diagnosis and does not automatically mean the operation failed. The next step is to identify the current pain generator, neurologic status, and realistic treatment goal.
Quick orientation
What to know first
New neurologic deficits or systemic warning signs change the urgency.
SCS or DRG may enter selected discussions, but either requires an individualized diagnosis and treatment review.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
Spinal Cord Stimulation
May be considered within a trial-based neuromodulation pathway after cause-oriented reassessment and selection.
Alternatives, not a sequence
These options may be considered separately; one does not automatically lead to another.
Selected alternative
Dorsal Root Ganglion (DRG) Stimulation
Potential alternative for selected focal neuropathic presentations after reassessment.
Symptoms are clues, not a diagnosis
What persistent post-surgical spine pain can feel like
Symptoms help define the pattern but do not confirm the diagnosis by themselves. Distribution, timing, neurologic findings, and important alternatives shape the evaluation.
Persistent back or leg pain after expected healing
Burning, electric, or shooting leg pain
Reduced walking, sleep, or activity tolerance
Relevant anatomy
What causes persistent post-surgical spine pain
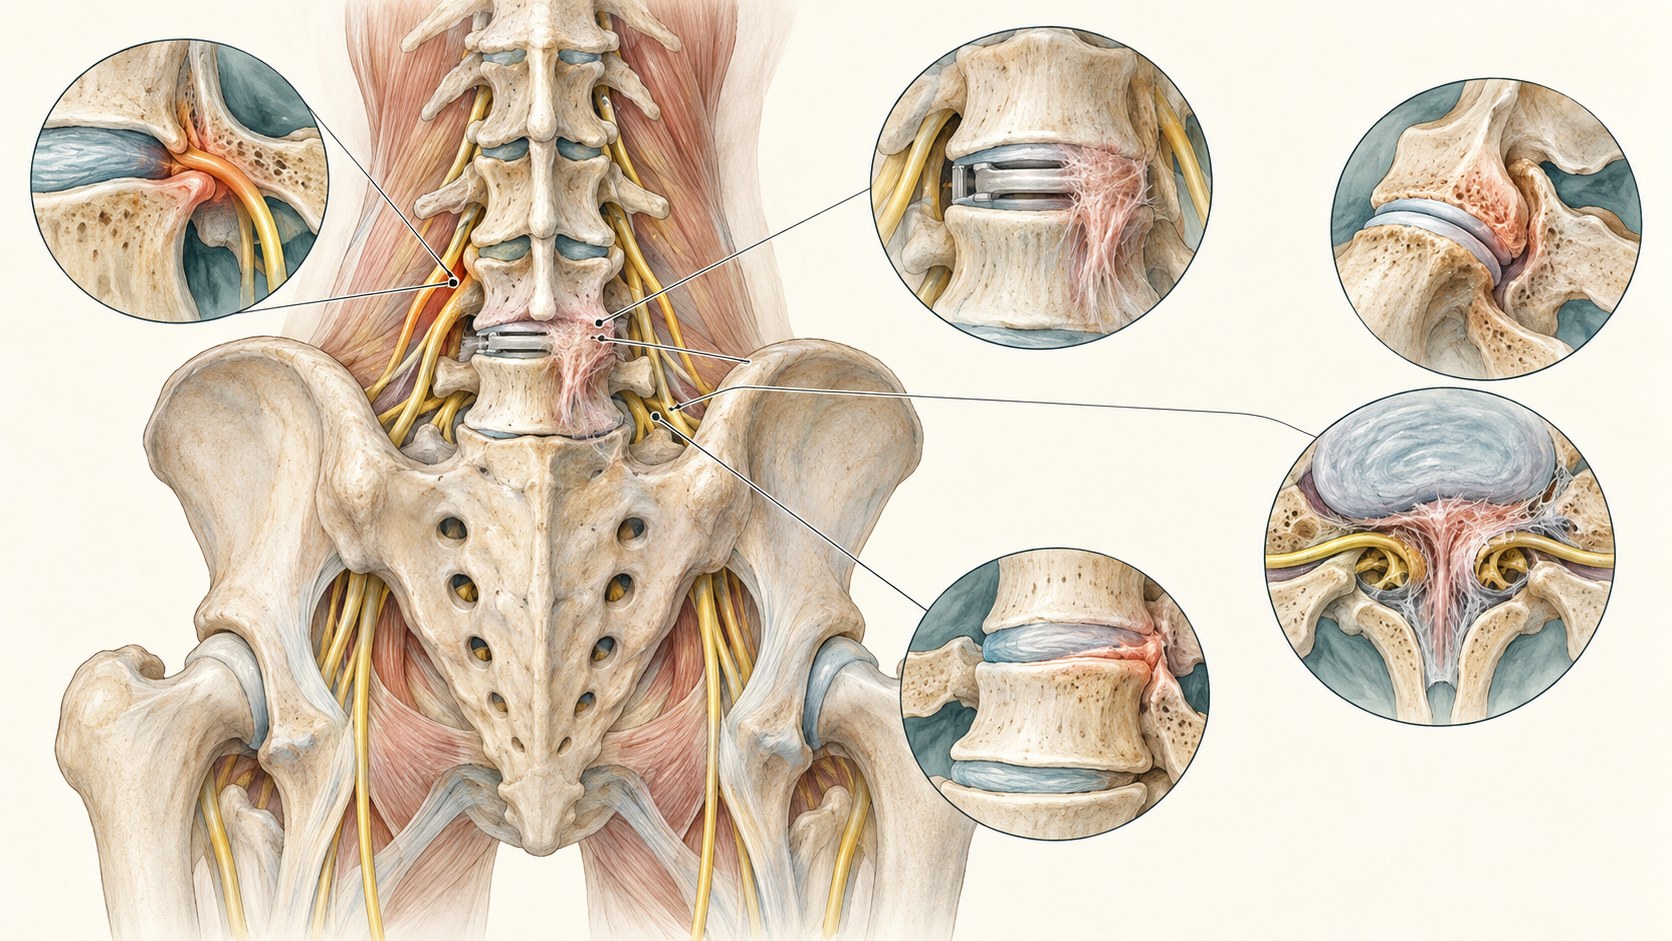
Potential contributors include residual or recurrent neural compression, nerve injury, scar-related change, adjacent-level disease, sacroiliac or facet pain, hardware or fusion concerns, and central sensitization. A label alone does not select a procedure.
History and examination first
How persistent post-surgical spine pain is diagnosed
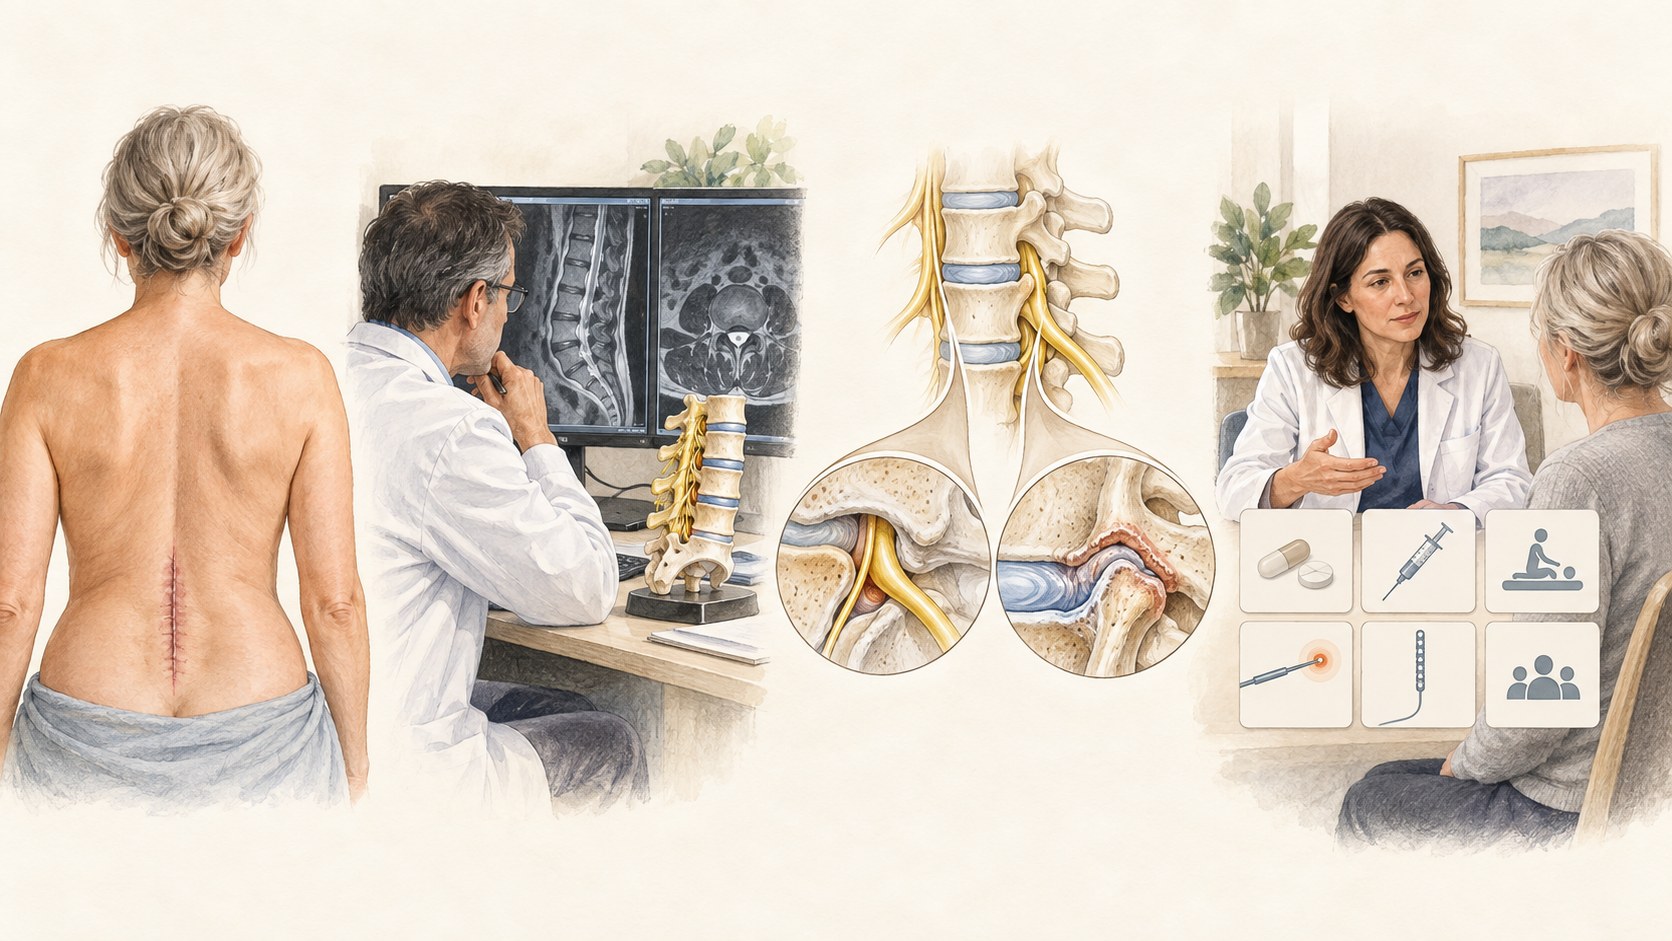
Evaluation reviews the operative history, symptom timing, pain distribution, neurologic findings, imaging, rehabilitation, and prior procedures. New weakness, bowel or bladder change, fever, wound concerns, or major trauma can require urgent assessment.
Keep the differential open
Conditions that can feel like persistent post-surgical spine pain
A safe diagnosis keeps common and serious alternatives open until the history and examination support a narrower conclusion.
Recurrent or residual neural compression
Adjacent segment, facet, or sacroiliac pain
Hip or peripheral nerve disease
Infection, instability, fracture, or another surgical issue
Core care
Non-surgical care for persistent post-surgical spine pain
Procedure discussions belong inside a broader plan that protects function and addresses the underlying condition.
Rehabilitation matched to neurologic and structural findings
Medication and sleep review
Targeted diagnostic work-up when it will change care
Surgical reassessment when a correctable structural problem is suspected
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and patient selection affect how a finding should be used.
Terminology has shifted toward persistent spinal pain syndrome to avoid implying blame or a single mechanism.
Randomized SCS evidence applies to selected neuropathic patterns, not every postoperative pain presentation.
DRG evidence in this population remains limited.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, relevant anatomy, prior care, risk, alternatives, goals, and the evidence for the exact indication must align.
Referral and urgent signs
When persistent post-surgical spine pain needs urgent care
These findings can change the timing or destination of care.
New or progressive weakness
New bowel or bladder dysfunction or saddle numbness
Fever, drainage, or worsening wound concern
Severe new pain after trauma
The visit
Your first visit for persistent post-surgical spine pain
The visit should narrow the diagnosis, identify safety or referral needs, review prior care, and choose the next useful decision rather than defaulting to a procedure.
Review surgery and symptom timeline
Perform neurologic and mechanical examination
Decide whether updated imaging, surgical review, rehabilitation, or neuromodulation evaluation is appropriate
Common questions
Persistent Post-Surgical Spine Pain FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Does persistent pain mean my surgery failed?
No. Pain may persist or recur for several reasons, and the current cause needs to be reassessed without assuming blame or one mechanism.
Do I automatically need another surgery?
No. Repeat surgery is considered when a correctable structural problem matches the symptoms. Other pathways may be more appropriate.
Where can SCS fit?
SCS may be considered for selected chronic neuropathic pain after diagnosis, prior care, goals, and risks are reviewed.
Diagnosis before procedure
See a pain specialist for persistent post-surgical spine pain in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that best fits the clinical picture.
