
CRPS is a clinical diagnosis using multiple symptom and sign categories.
Nerve Pain
Complex Regional Pain Syndrome
Complex regional pain syndrome can involve pain that is disproportionate to the inciting event along with sensory, temperature, color, swelling, sweating, movement, or trophic changes. Diagnosis requires a pattern of symptoms and observed signs, not one test.
Quick orientation
What to know first
Other explanations must be considered.
Functional restoration is central; SCS and DRG are selected later-pathway options.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
Spinal Cord Stimulation
May be considered within a trial-based neuromodulation pathway after multidisciplinary diagnosis and selection.
Treatment option
Dorsal Root Ganglion (DRG) Stimulation
May be considered for selected focal CRPS presentations within a trial-based pathway.
Alternatives, not a sequence
These options may be considered separately; one does not automatically lead to another.
Selected alternative
Peripheral Nerve Stimulation
Potential alternative only when a target-specific peripheral pathway is established.
Selected alternative
Stellate Ganglion Block
Alternative consideration only for selected upper-extremity CRPS presentations within multidisciplinary care; this edge does not apply to every CRPS presentation.
Selected alternative
Supraclavicular Brachial Plexus Block
Alternative consideration for selected upper-extremity CRPS presentations within multidisciplinary management; not routine, universally applicable, or applicable to lower-extremity CRPS.
Selected alternative
Sciatic Nerve Block
Alternative consideration for selected lower-extremity CRPS presentations within multidisciplinary care; not routine, first-line, universally applicable, or applicable to upper-extremity CRPS.
Symptoms are clues, not a diagnosis
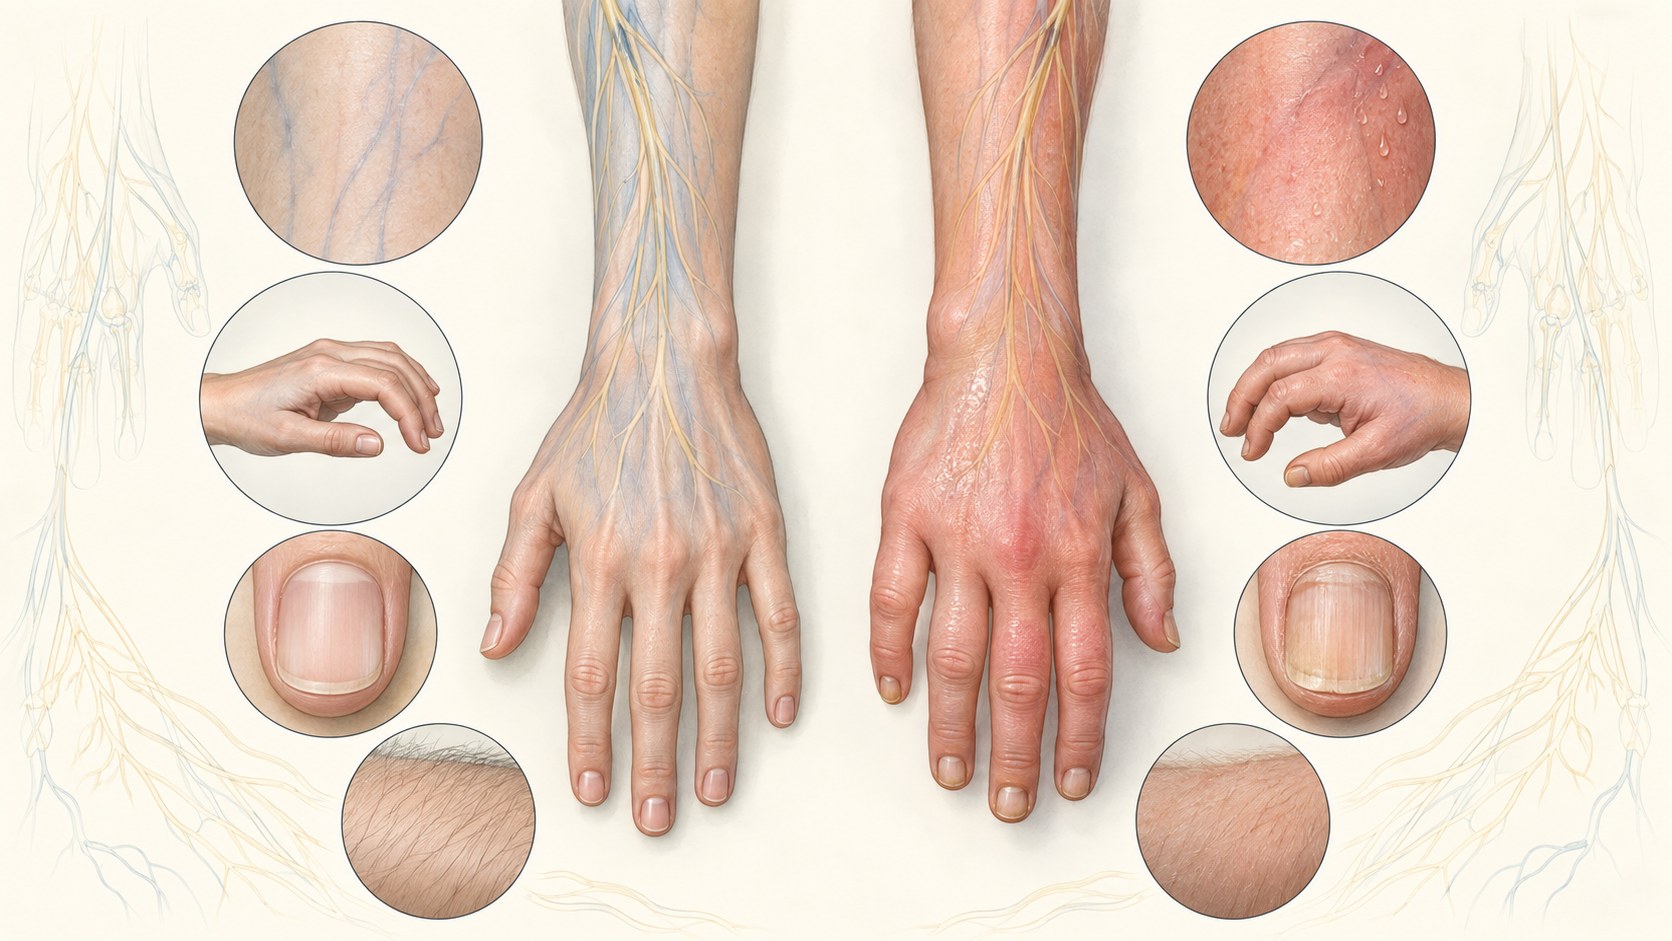
What CRPS can feel like
Symptoms help define the pattern but do not confirm the diagnosis by themselves. Distribution, timing, neurologic findings, and important alternatives shape the evaluation.
Pain disproportionate to the expected course
Sensitivity to light touch or temperature
Color, temperature, swelling, or sweating asymmetry
Reduced motion, weakness, tremor, or nail and hair change
Relevant anatomy
What causes CRPS
CRPS reflects interacting sensory, autonomic, motor, inflammatory, and central nervous system changes. It may follow injury or surgery, but the severity and persistence exceed what is expected from the initial event.
History and examination first
How CRPS is diagnosed
The Budapest framework requires symptoms across categories and observed signs at evaluation, plus no better diagnosis. Findings can fluctuate, so history, serial examination, and focused testing may be needed to exclude alternatives.

Keep the differential open
Conditions that can feel like CRPS
A safe diagnosis keeps common and serious alternatives open until the history and examination support a narrower conclusion.
Ongoing tissue injury or infection
Vascular or lymphatic disease
Entrapment or generalized neuropathy
Inflammatory, rheumatologic, or functional neurologic conditions
Core care
Non-surgical care for CRPS
Procedure discussions belong inside a broader plan that protects function and addresses the underlying condition.
Early graded functional restoration and desensitization
Physical or occupational therapy paced to avoid immobilization
Medication and psychological support matched to the person
Procedures used to support function when the rationale is clear
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and patient selection affect how a finding should be used.
Budapest criteria improve specificity compared with older criteria but remain clinical.
A five-year SCS randomized follow-up found diminishing group differences over time.
DRG had higher treatment success than conventional SCS in the ACCURATE selected lower-limb population.
PNS evidence remains limited and heterogeneous.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, relevant anatomy, prior care, risk, alternatives, goals, and the evidence for the exact indication must align.
Referral and urgent signs
When CRPS needs urgent care
These findings can change the timing or destination of care.
A cold or pulseless limb
Fever, drainage, or rapidly spreading redness
New major weakness or concern for compartment syndrome
The visit
Your first visit for CRPS
The visit should narrow the diagnosis, identify safety or referral needs, review prior care, and choose the next useful decision rather than defaulting to a procedure.
Document symptoms and observed signs across categories
Exclude a better explanation
Build a function-centered plan and revisit neuromodulation only after selection review
Common questions
Complex Regional Pain Syndrome FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is there one test for CRPS?
No. Diagnosis uses the clinical pattern, observed signs, and exclusion of a better explanation. Tests may help evaluate alternatives.
Why is movement part of treatment?
Prolonged protection can worsen loss of function. Carefully graded restoration and desensitization aim to improve use without ignoring symptom severity.
How do SCS and DRG differ?
SCS targets broader spinal pathways. DRG targets selected sensory ganglia and has comparative evidence in a selected lower-limb CRPS and causalgia population.
How soon should CRPS be evaluated?
Early evaluation is recommended. Early assessment can help establish the diagnosis and allow movement-based rehabilitation, desensitization and pain treatment to start sooner, while other causes of a painful, swollen or discolored limb are checked. It helps to bring details of the injury or surgery that came before the symptoms and the treatments already tried.
Where can I be seen for CRPS?
New-patient visits are available at the Allen office, Monday to Friday, and at the Wylie office on Tuesdays. Spinal cord and DRG stimulation trials and implants, and other image-guided procedures, are performed in Allen.
Diagnosis before procedure
See a pain specialist for CRPS in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that best fits the clinical picture.
