
The symptom region is a starting point, not a diagnosis.
Shoulder, elbow & arm conditions
Shoulder Pain
Shoulder Pain can reflect several different structures and mechanisms. The location and quality of symptoms help organize the evaluation, but they do not establish one diagnosis or treatment path.
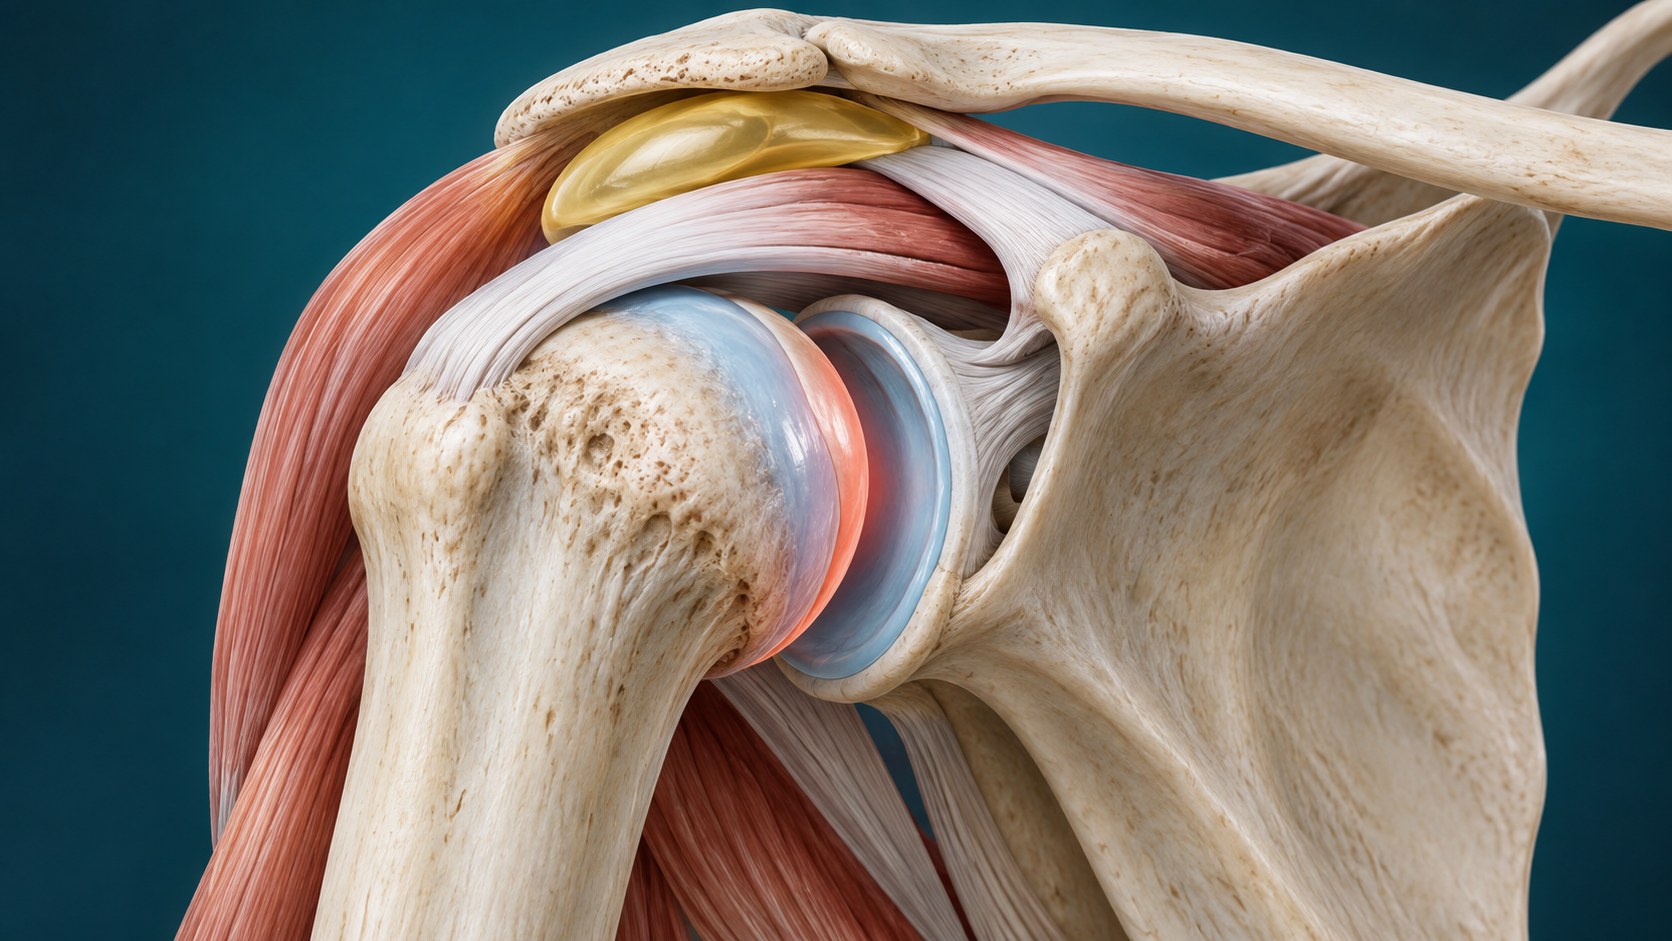
Quick orientation
What to know first
History and examination determine which anatomy and tests matter.
Urgent, neurologic, infectious, vascular, traumatic, and systemic causes stay visible until reasonably excluded.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
Suprascapular Nerve Block
For selected chronic shoulder pain, including arthritis
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
Shoulder Joint Injection
For selected shoulder joint arthritis or inflammation; relief is temporary and does not repair structure
Treatment option
Trigger Point Injection
For clinically identified muscle trigger points around the shoulder blade
May come later
A later procedure is considered only when evaluation and the response to earlier steps support it.
Later treatment option
Suprascapular Radiofrequency Treatment
For selected persistent shoulder pain after a supportive block; evidence is limited, and pulsed and thermal techniques differ
Choose the guide that matches your question
Explore the specific guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Clinical guide
Shoulder Osteoarthritis
Shoulder-joint osteoarthritis symptoms, evaluation, conservative care, and procedure considerations.
Open this guideClinical guide
Rotator Cuff Tendinopathy
Rotator-cuff tendon pain and dysfunction, differential diagnosis, rehabilitation, and procedure considerations.
Open this guideSymptom guide
Elbow Pain
Elbow-pain orientation across lateral, medial, anterior/posterior, tendon, joint, nerve, referred, and traumatic causes.
Open this guideClinical guide
Cervical Radiculopathy
Cervical nerve-root symptoms into the shoulder, arm, or hand and their evaluation and treatment pathways.
Open this guideSymptoms are clues, not a diagnosis
What shoulder pain can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Location, radiation, timing, quality, sensory change, weakness, stiffness, swelling, activity, position, sleep, and function help define the pattern.
Similar symptoms may arise from a joint, tendon, muscle, spine, peripheral nerve, circulation, or systemic condition.
Imaging and test abnormalities require clinical correlation and may not identify the symptom source.
Relevant anatomy
What causes shoulder pain
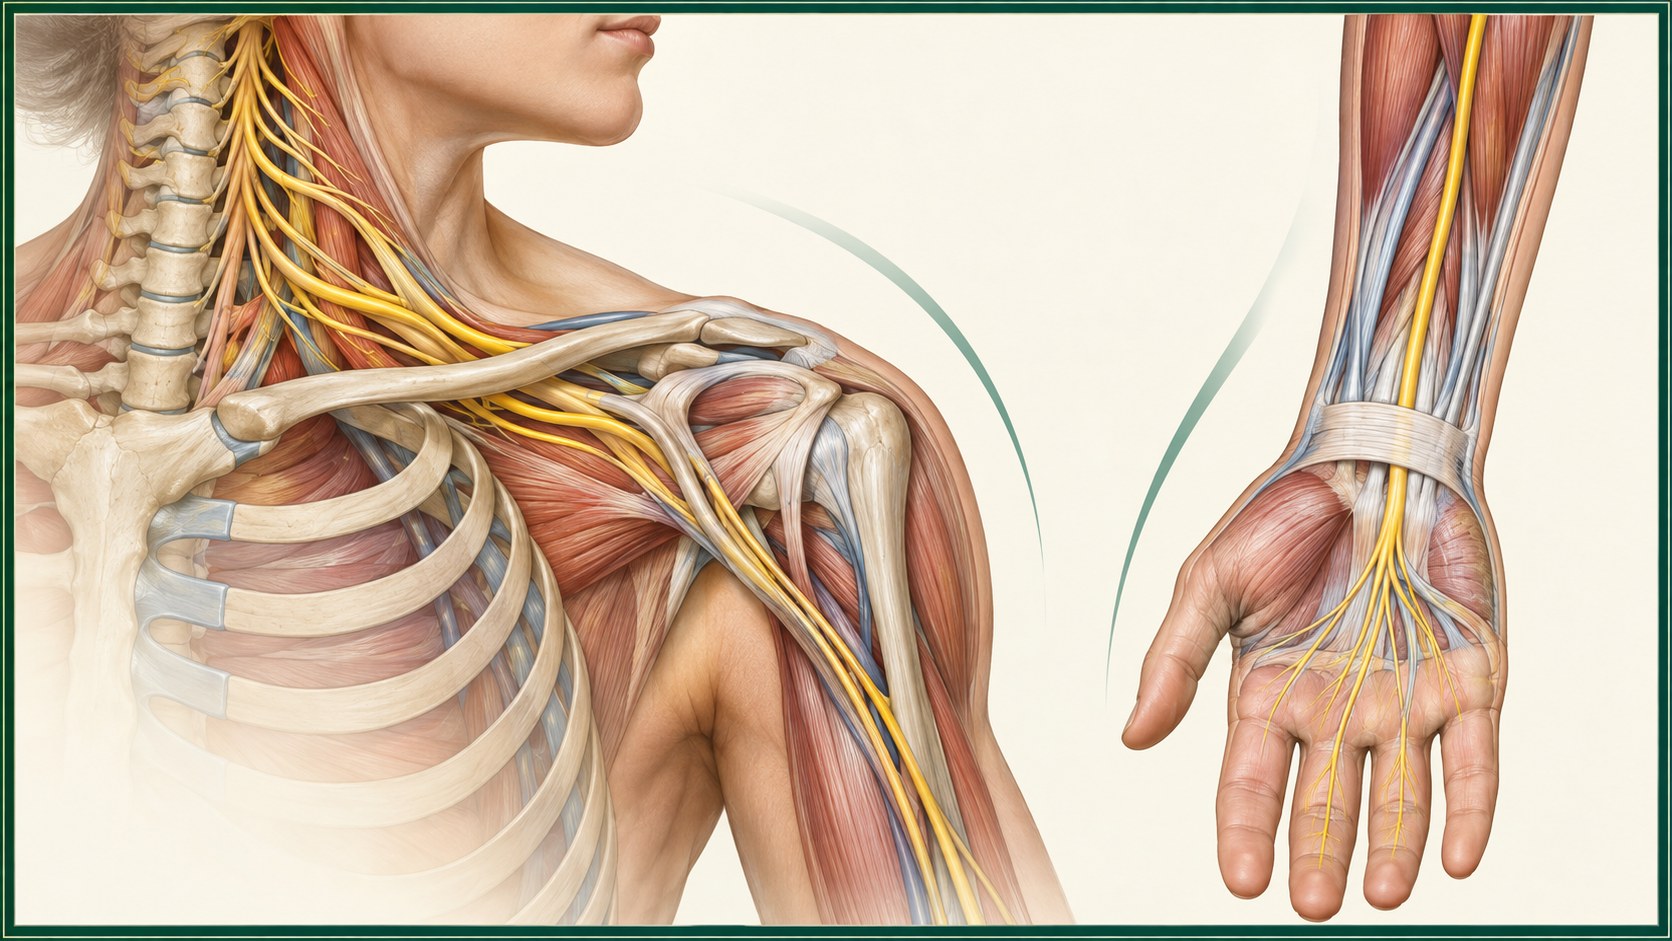
The region includes joints, muscles, tendons, nerves, blood vessels, and possible referral pathways. Their symptom territories overlap, so the examination and selective testing must answer a defined clinical question.
History and examination first
How shoulder pain is diagnosed
Evaluation begins with the patient question, safety screen, history, and focused examination. Testing is selected only when it can clarify a competing diagnosis, guide treatment, or change referral urgency.
Keep the differential open
Conditions that can feel like shoulder pain
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Local joint, tendon, muscle, ligament, bursa, bone, or soft-tissue disorders
Spinal referral, nerve-root, plexus, or peripheral-nerve disorders
Traumatic, infectious, inflammatory, vascular, metabolic, medication-related, or oncologic causes
Core care
Non-surgical care for shoulder pain
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education, pacing, sleep and activity strategies matched to the diagnosis
Rehabilitation focused on mobility, strength, tolerance, and function when safe
Medication and comorbidity review with the appropriate clinician
Reassessment when symptoms, neurologic findings, function, or response changes
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Guidelines support question-specific imaging rather than routine testing for every presentation.
Clinical correlation is required because structural findings may be present without being the symptom source.
Treatment evidence applies to defined diagnoses and cannot be generalized to undifferentiated regional pain.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When shoulder pain needs urgent care
These findings can change the timing or destination of care.
A visibly deformed joint, major trauma, inability to bear weight or use the limb, or rapidly increasing swelling
A hot red joint, fever, spreading redness, open wound, or concern for infection
New limb weakness, loss of sensation, a cold or pale limb, marked calf swelling, chest symptoms, or another vascular or neurologic emergency
The visit
Your first visit for shoulder pain
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the location, timing, triggers, sensory features, functional effect, prior injury, and prior care
Examine the relevant joint, spine, muscles, nerves, circulation, gait, strength, sensation, and reflexes as appropriate
Use imaging, electrodiagnostic testing, laboratory work, or referral only when it answers a clinical question
Choose education, rehabilitation, medical care, further diagnostic work, a selected procedure discussion, or referral based on the working diagnosis
Common questions
Shoulder Pain FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
For Shoulder Pain, does the location alone establish the diagnosis?
No. Several tissues and referred pathways can produce pain in the same region.
Do I always need imaging for Shoulder Pain?
No. Testing is chosen when it can answer a clinical question or change care.
Why is a treatment guide listed with Shoulder Pain?
Related guides are educational and do not establish a diagnosis or treatment recommendation.
Diagnosis before procedure
See a pain specialist for shoulder pain in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
