
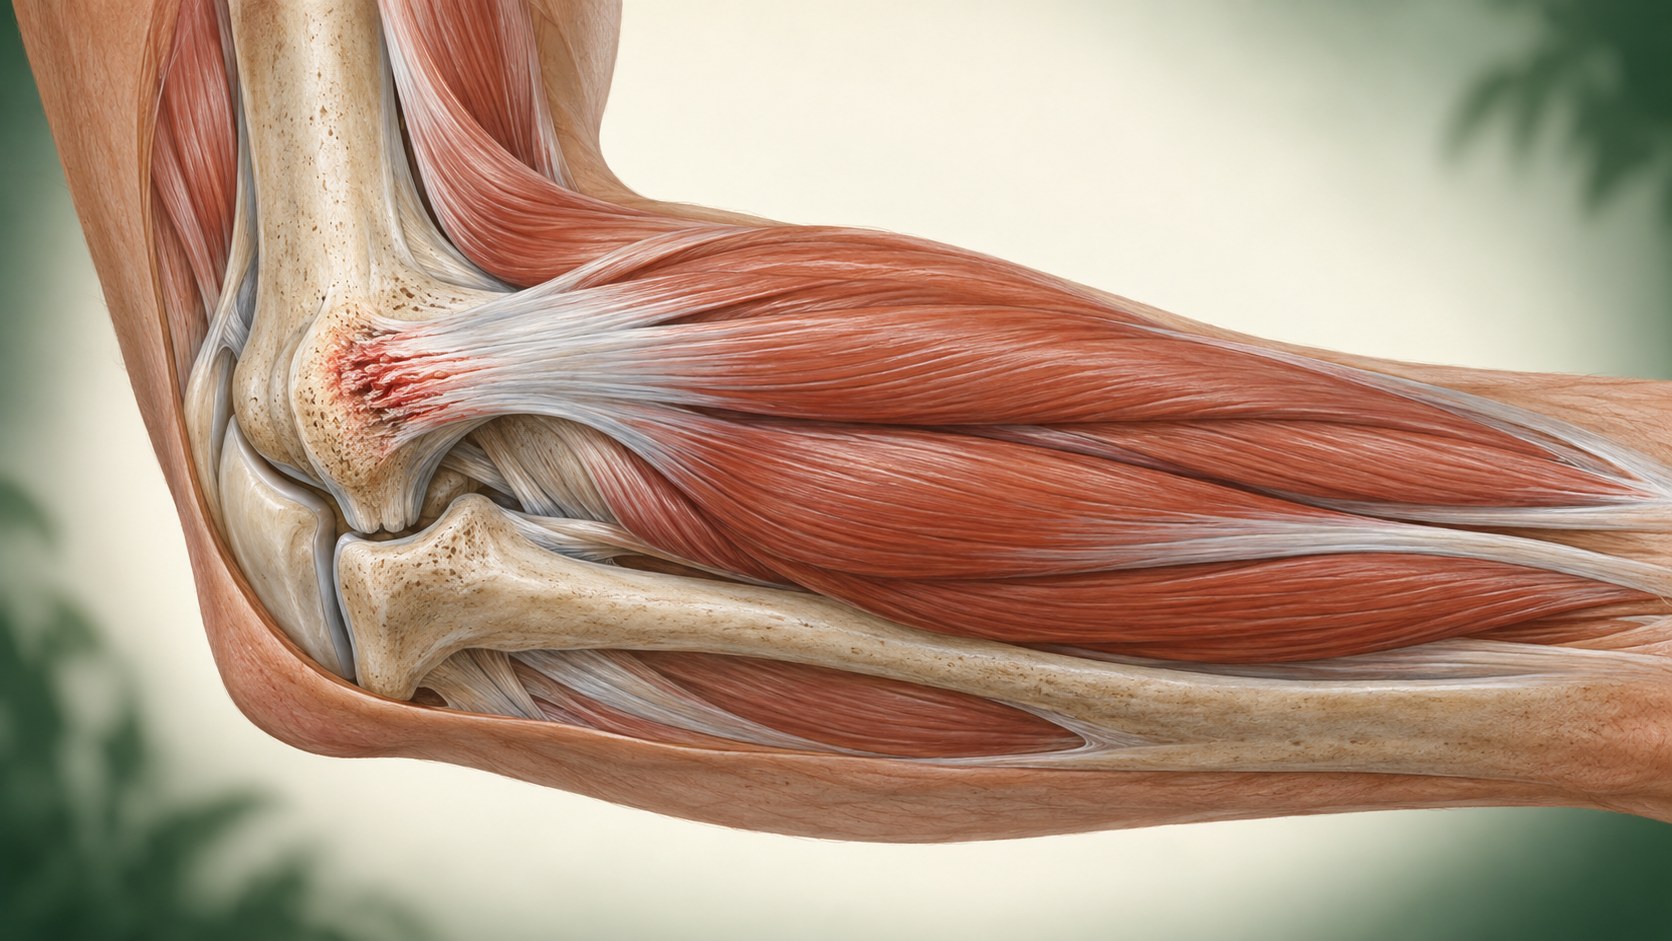
The common extensor tendon attaches forearm muscles to the outside of the elbow.
Shoulder, Elbow & Arm · Tennis Elbow
Lateral Epicondylitis
Pain at the outside of the elbow often begins with gripping, lifting, or repeated wrist use. Lateral epicondylitis is one possible cause, but the location alone does not establish the diagnosis.
Quick orientation
What to know first
Pain with gripping is a clue, not proof. Nerve and referred pain can feel similar.
Rehabilitation and load adjustment usually come before an injection discussion.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
Platelet-Rich Plasma (PRP)
PRP may be discussed only after diagnosis-specific evidence, alternatives, and individual patient factors are reviewed.
Symptoms are clues, not a diagnosis
What lateral epicondylitis can feel like
Symptoms help define the pattern and show which daily, work, or athletic demands are difficult. They also guide the physical examination. No single symptom, tender spot, or self-test confirms the diagnosis, so a clinician still needs to consider nearby joints, nerves, referred pain, and other tissue problems.
Tenderness near the lateral epicondyle
Pain with gripping, lifting, or resisted wrist extension
Reduced grip tolerance that may be worse with the elbow straight
Relevant anatomy
What causes lateral epicondylitis
The common extensor tendon anchors several wrist and finger extensor muscles at the lateral epicondyle. Symptoms are commonly linked to tendon overload and disorganized tendon change rather than a simple short-lived inflammation.
History and examination first
How lateral epicondylitis is diagnosed
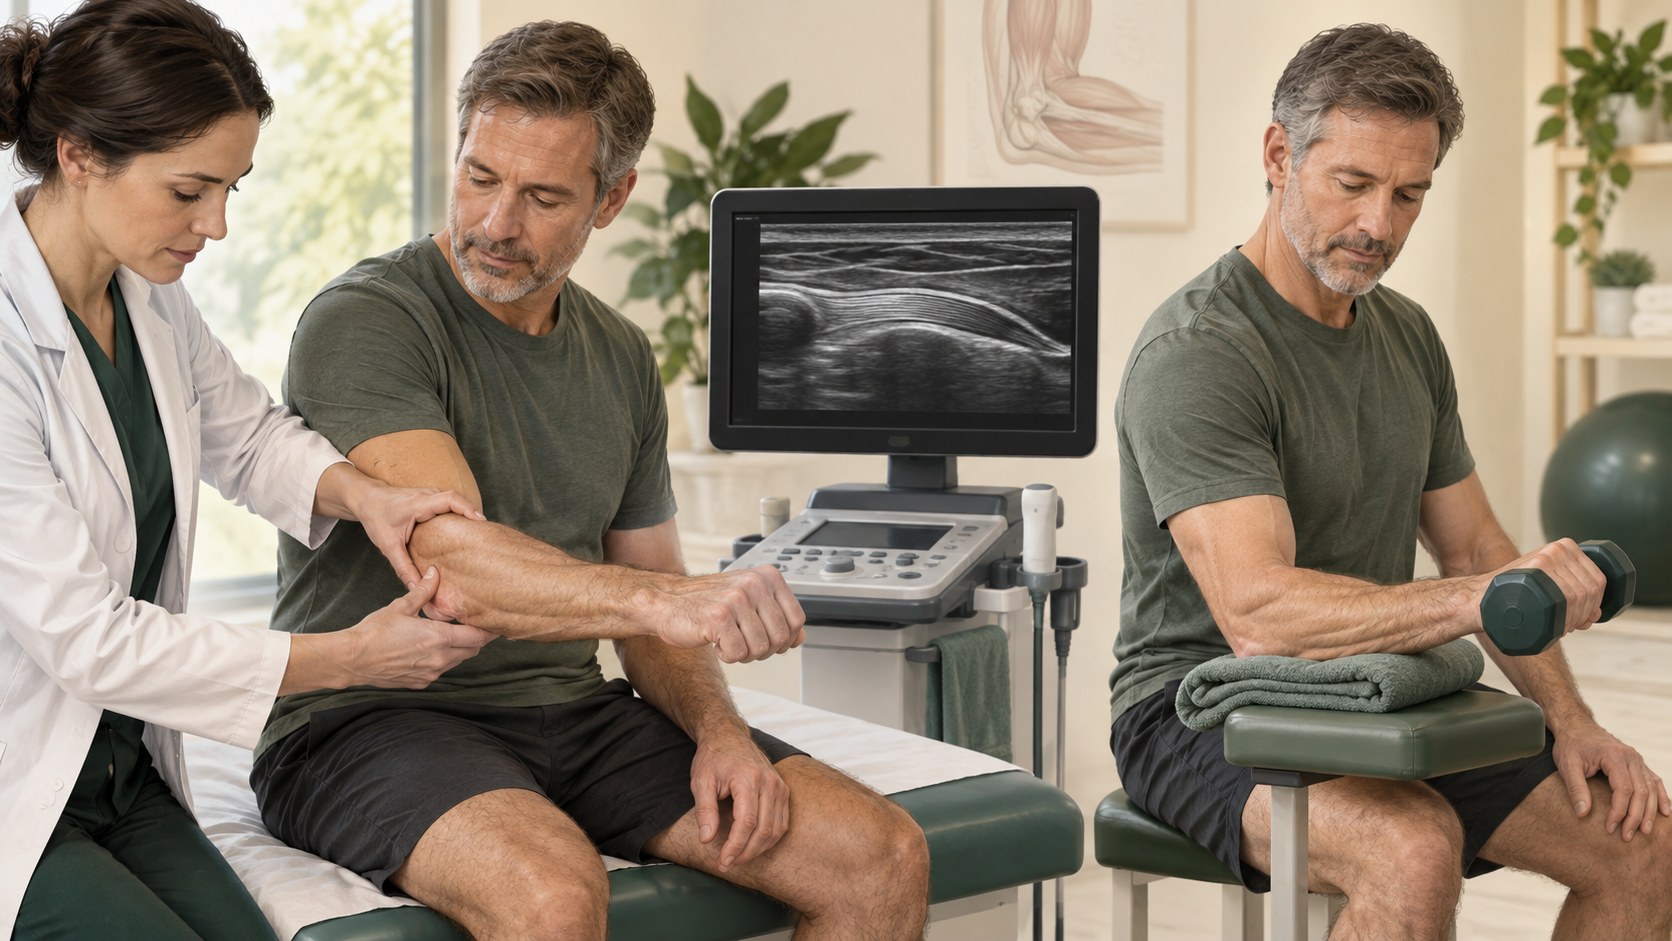
Evaluation combines the story, the exact tender area, grip and resisted-wrist testing, elbow motion, and a neurologic screen. Ultrasound or MRI may help when the diagnosis is uncertain, symptoms persist, or a tear or another condition is suspected.
Keep the differential open
Conditions that can feel like lateral epicondylitis
A diagnosis is safer when the common alternatives are considered instead of treating pain location as proof.
- Radial tunnel or posterior interosseous nerve irritation
- Pain referred from the neck
- Elbow joint disease or instability
- A tendon tear or another local soft-tissue problem
Core care
Non-surgical care for lateral epicondylitis
Care should build capacity and reduce unnecessary protection while staying responsive to the exact diagnosis and symptom behavior.
Adjust the activities and tools that repeatedly provoke symptoms
Progress wrist-extensor and grip loading rather than relying on rest alone
Use bracing, manual therapy, or pain-relieving measures selectively
Reassess the diagnosis when progress stalls
Evidence at a glance
Evidence at a glance
The evidence is not a scoreboard. Comparator choice, follow-up, patient selection, and the exact tissue problem can change the result.
Exercise may improve mid-term pain, but certainty and optimal dosing remain limited.
Corticosteroid can look better early in some comparisons, while recurrence and longer-term results complicate that short-term benefit.
PRP studies conflict. Comparisons with corticosteroid may favor PRP later, while placebo-controlled trials have found no clear benefit.
Decision quality matters
Evidence, limits, and who it may fit
Procedure consideration requires a confirmed diagnosis, correlation between symptoms and anatomy, review of prior care, contraindications, alternatives, goals, and the limits of the diagnosis-specific evidence. Relationship membership does not establish candidacy.
- Exercise may improve mid-term pain, but certainty and optimal dosing remain limited.
- Corticosteroid can look better early in some comparisons, while recurrence and longer-term results complicate that short-term benefit.
- PRP studies conflict. Comparisons with corticosteroid may favor PRP later, while placebo-controlled trials have found no clear benefit.
Referral and urgent signs
When lateral epicondylitis needs urgent care
Some findings should redirect the plan toward urgent care, another specialist, or a different diagnosis.
- A sudden pop, bruising, or major new weakness
- Progressive numbness or hand weakness
- A hot, swollen joint, fever, or recent major trauma
The visit
Your first visit for lateral epicondylitis
The visit should narrow the diagnosis, clarify what has already been tried, and identify the next useful decision rather than defaulting to an injection. That may mean refining a rehabilitation plan, obtaining imaging only when it would change care, discussing a procedure with its evidence limits, or arranging another specialist evaluation.
Clarify the exact pain pattern and work or sport demands
Examine the elbow, wrist, neck, strength, and nerve findings
Review prior rehabilitation and decide whether imaging would change care
Common questions
Lateral Epicondylitis FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is tennis elbow always caused by tennis?
No. Repetitive gripping, lifting, tools, racquet sports, and abrupt changes in workload can all contribute. Some patients cannot identify one trigger.
Do I need an MRI?
Usually not at the first visit. Imaging is most useful when the diagnosis is uncertain, symptoms do not follow the expected course, or a tear or another cause is suspected.
Is PRP the first treatment?
Usually no. A progressive loading program and activity adjustment are central. PRP may be discussed for selected persistent cases after the diagnosis and prior care are reviewed.
Diagnosis before procedure
See a pain specialist for lateral epicondylitis in Allen, TX
The next step is to confirm the pain source, review prior care, and choose a plan that fits the diagnosis and your goals.
