
The symptom region is a starting point, not a diagnosis.
Neck conditions
Neck Pain
Neck Pain can reflect several different structures and mechanisms. The location and quality of symptoms help organize the evaluation, but they do not establish one diagnosis or treatment path.
Quick orientation
What to know first
History and examination determine which anatomy and tests matter.
Urgent, neurologic, infectious, vascular, traumatic, and systemic causes stay visible until reasonably excluded.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
Cervical Medial Branch Block
Diagnostic block when neck facet-joint pain is suspected
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
Cervical Epidural Steroid Injection
For selected arm pain from a pinched neck nerve root, not neck pain alone; rare serious complications require careful selection
Treatment option
Trigger Point Injection
For clinically identified muscle trigger points in the neck and shoulders
May come later
A later procedure is considered only when evaluation and the response to earlier steps support it.
Later treatment option
Cervical Radiofrequency Ablation
For selected facet-joint neck pain after positive diagnostic blocks; relief is not guaranteed or permanent
Choose the guide that matches your question
Explore the specific guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Clinical guide
Cervical Spondylosis
Degenerative cervical-spine changes when they are clinically relevant to symptoms, evaluation, and care.
Open this guideClinical guide
Cervical Facet Joint Pain
Region-specific cervical facet-mediated pain, diagnostic medial branch block considerations, and possible RFA pathway.
Open this guideClinical guide
Cervical Spinal Stenosis
Cervical canal narrowing, possible cord or nerve effects, gait/hand warning features, and referral-aware evaluation.
Open this guideClinical guide
Cervical Radiculopathy
Cervical nerve-root symptoms into the shoulder, arm, or hand and their evaluation and treatment pathways.
Open this guideCare overview
Headache Disorders
Orientation for patients researching recurrent or persistent headache patterns and the practice's evaluation/referral boundaries.
Open this guideSymptoms are clues, not a diagnosis
What neck pain can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Location, radiation, timing, quality, sensory change, weakness, stiffness, swelling, activity, position, sleep, and function help define the pattern.
Similar symptoms may arise from a joint, tendon, muscle, spine, peripheral nerve, circulation, or systemic condition.
Imaging and test abnormalities require clinical correlation and may not identify the symptom source.
Relevant anatomy
What causes neck pain
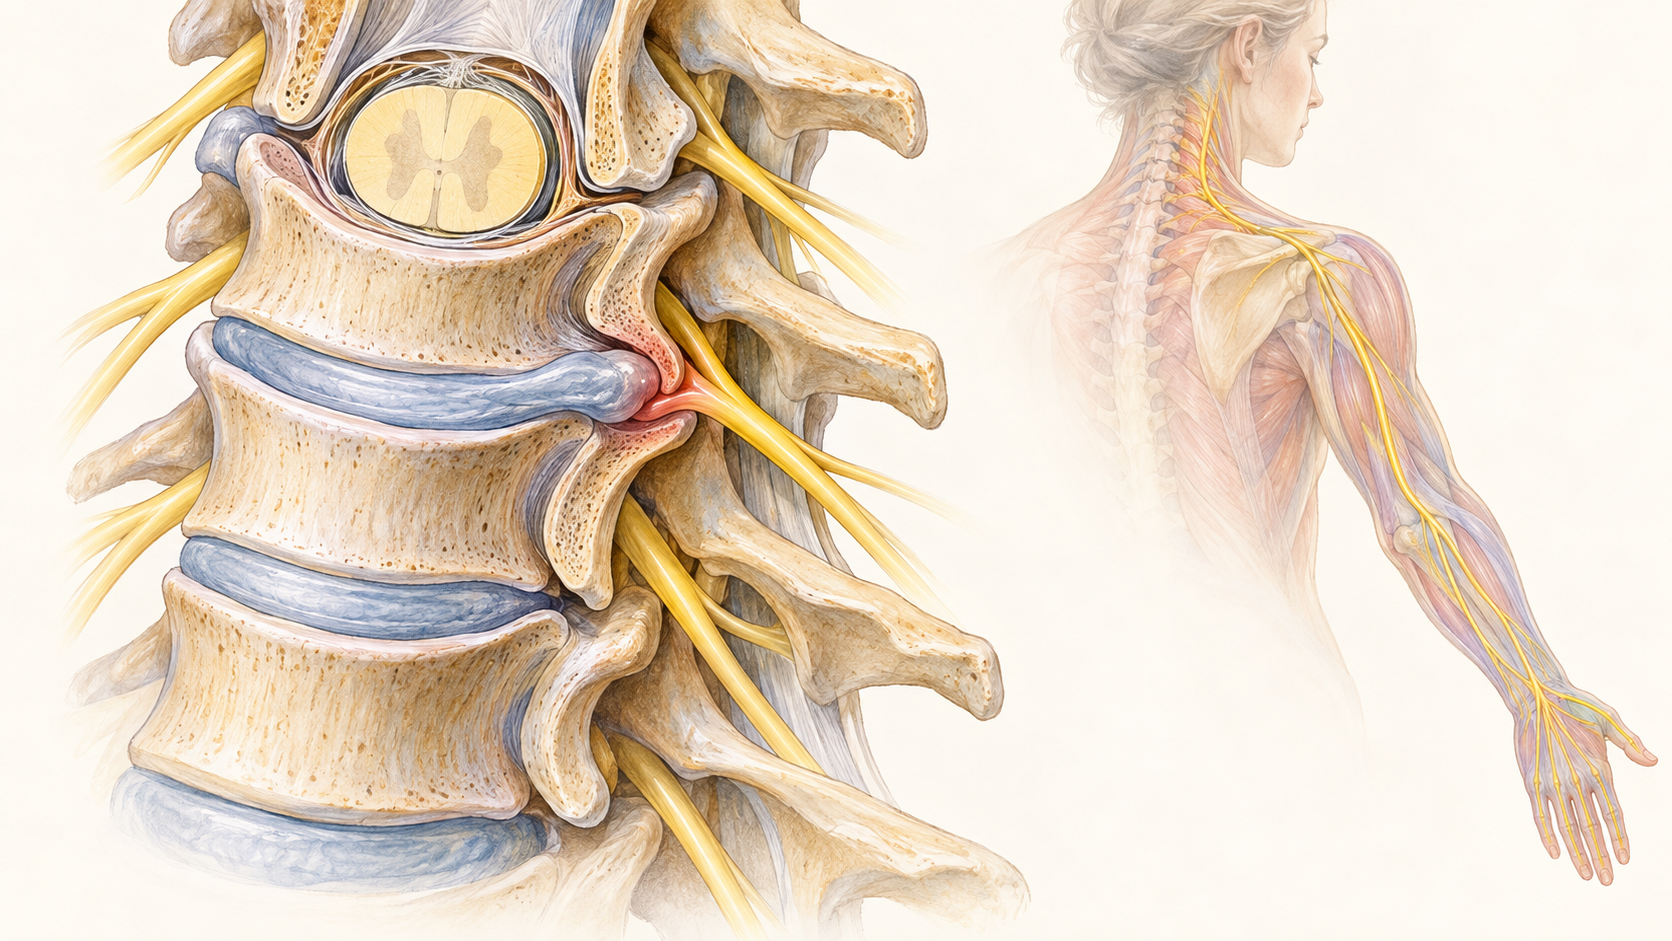
The region includes joints, muscles, tendons, nerves, blood vessels, and possible referral pathways. Their symptom territories overlap, so the examination and selective testing must answer a defined clinical question.
History and examination first
How neck pain is diagnosed
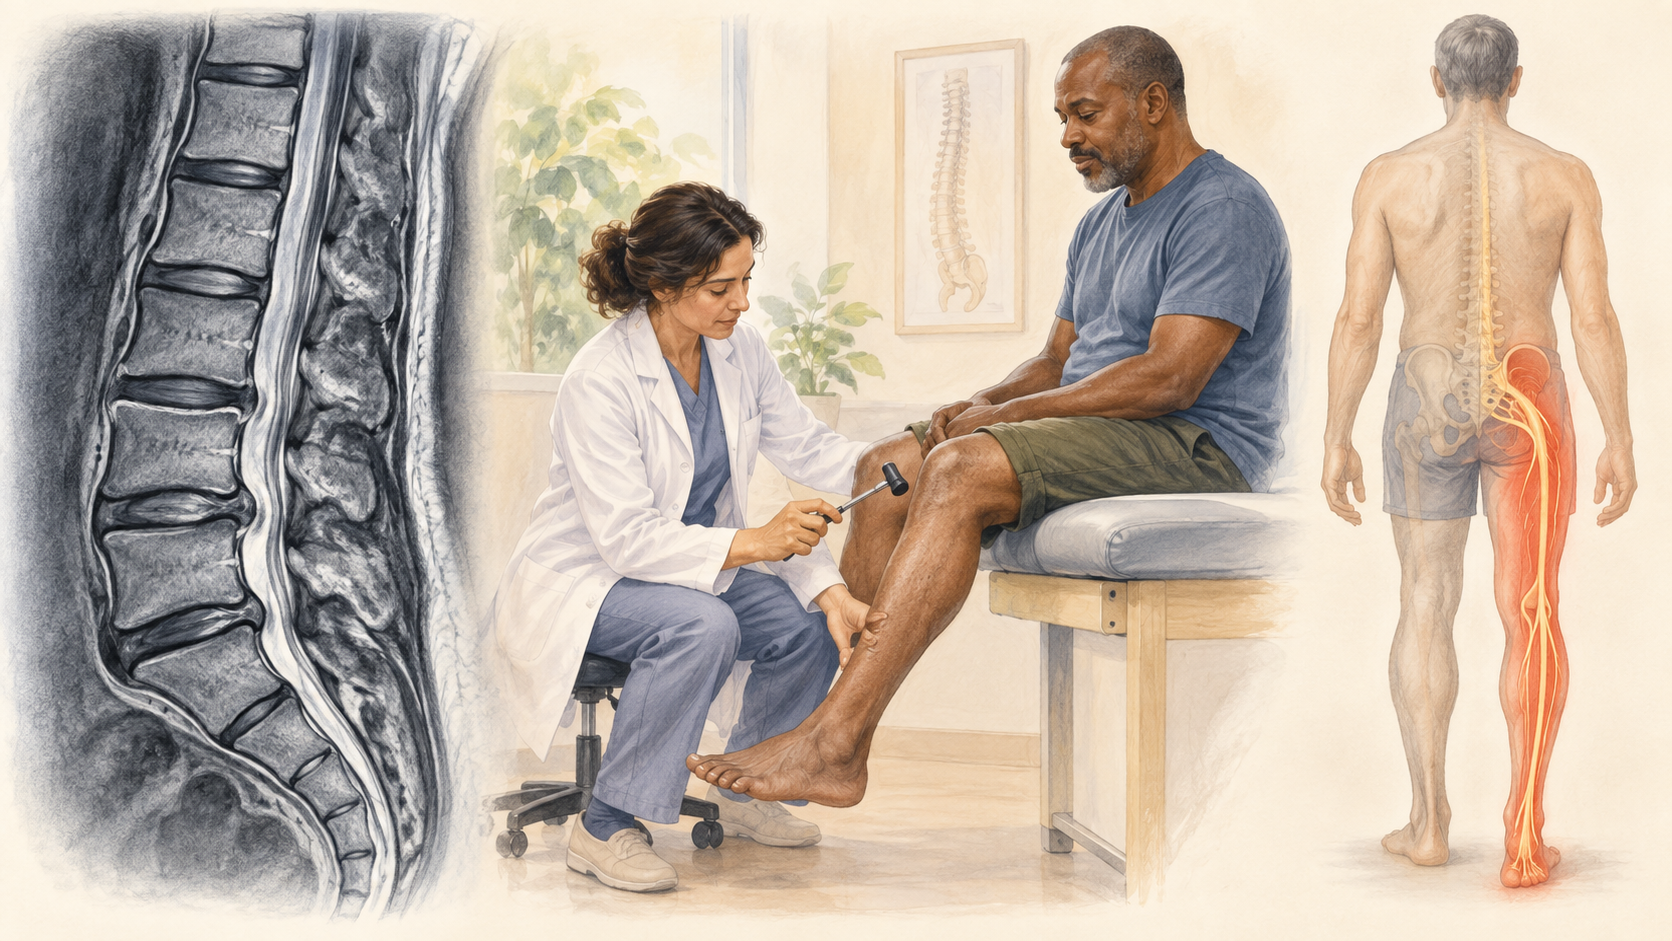
Evaluation begins with the patient question, safety screen, history, and focused examination. Testing is selected only when it can clarify a competing diagnosis, guide treatment, or change referral urgency.
Keep the differential open
Conditions that can feel like neck pain
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Local joint, tendon, muscle, ligament, bursa, bone, or soft-tissue disorders
Spinal referral, nerve-root, plexus, or peripheral-nerve disorders
Traumatic, infectious, inflammatory, vascular, metabolic, medication-related, or oncologic causes
Core care
Non-surgical care for neck pain
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education, pacing, sleep and activity strategies matched to the diagnosis
Rehabilitation focused on mobility, strength, tolerance, and function when safe
Medication and comorbidity review with the appropriate clinician
Reassessment when symptoms, neurologic findings, function, or response changes
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Guidelines support question-specific imaging rather than routine testing for every presentation.
Clinical correlation is required because structural findings may be present without being the symptom source.
Treatment evidence applies to defined diagnoses and cannot be generalized to undifferentiated regional pain.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When neck pain needs urgent care
These findings can change the timing or destination of care.
New or worsening arm or hand weakness, loss of hand coordination, balance change, gait difficulty, or widespread numbness that may suggest spinal cord involvement
New bowel or bladder dysfunction together with limb weakness, gait change, or other signs of spinal cord dysfunction
Fever, major trauma, cancer history, unexplained weight loss, severe night pain, or another concern for infection, fracture, inflammatory disease, or cancer
The visit
Your first visit for neck pain
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the location, timing, triggers, sensory features, functional effect, prior injury, and prior care
Examine the relevant joint, spine, muscles, nerves, circulation, gait, strength, sensation, and reflexes as appropriate
Use imaging, electrodiagnostic testing, laboratory work, or referral only when it answers a clinical question
Choose education, rehabilitation, medical care, further diagnostic work, a selected procedure discussion, or referral based on the working diagnosis
Common questions
Neck Pain FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
When should I see a specialist for neck pain?
When pain lasts more than a few weeks, keeps returning, causes headaches, or comes with arm pain, numbness or weakness. Seek emergency care for new trouble with balance or walking, clumsy hands, bladder or bowel changes, severe neck pain after a significant injury, or fever with severe headache or neck stiffness.
What can cause ongoing neck pain?
Common sources include the facet joints, discs, nerve roots (cervical radiculopathy), muscles and age-related changes in the neck (cervical spondylosis). The pattern of symptoms and the examination help tell them apart.
Do I need an MRI for neck pain?
Not always. An MRI is usually considered when there are nerve or spinal cord symptoms, after an injury when the nerves, spinal cord or soft tissues need to be assessed, with other warning signs, or when the result would change the treatment plan.
Where can I be seen for neck pain?
New-patient visits are available at the Allen office, Monday to Friday, and at the Wylie office on Tuesdays. Image-guided neck procedures, such as cervical epidural steroid injections, medial branch blocks and radiofrequency ablation, are performed in Allen.
Diagnosis before procedure
See a pain specialist for neck pain in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
