
The target is selected from a concordant radicular pattern, not from imaging alone.
Epidural steroid injections
Caudal Epidural Steroid Injection
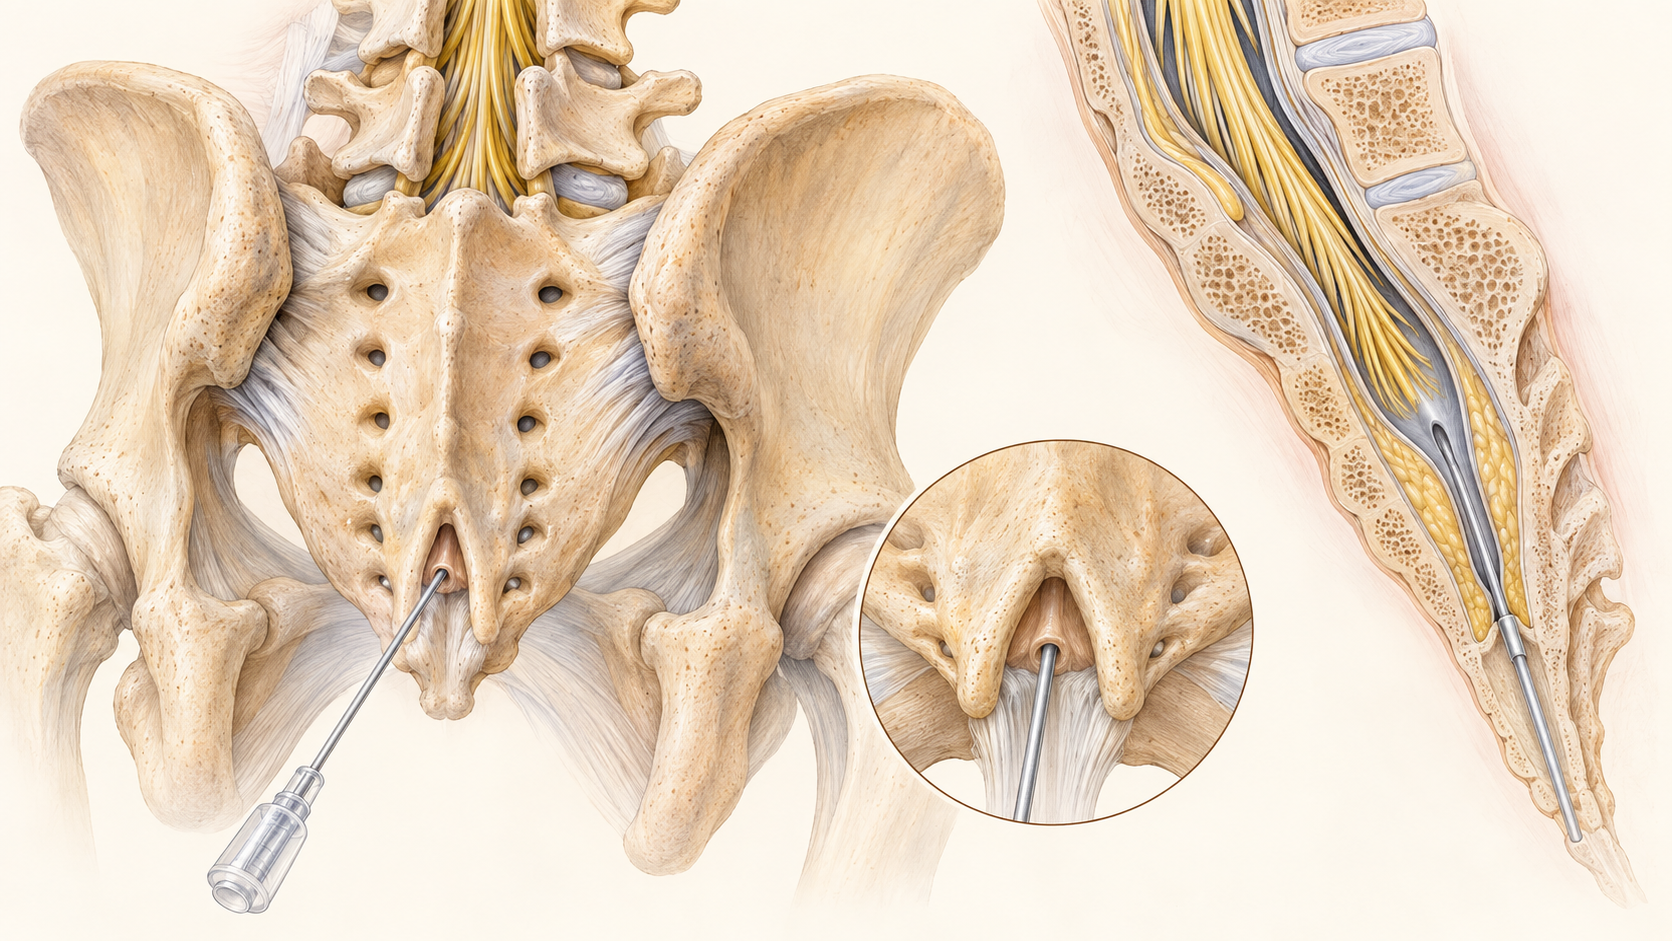
A caudal epidural injection enters the lower epidural space through the sacral hiatus. It may be considered when the target, anatomy, prior surgery, and clinical plan support that route, but it is not automatically broader, safer, or more effective.
Quick orientation
What to know first
Any average benefit is generally modest and more evident in the short term.
Epidural corticosteroid use is off-label and rare serious neurologic harms have been reported.
Target and mechanism
What a caudal epidural steroid injection targets
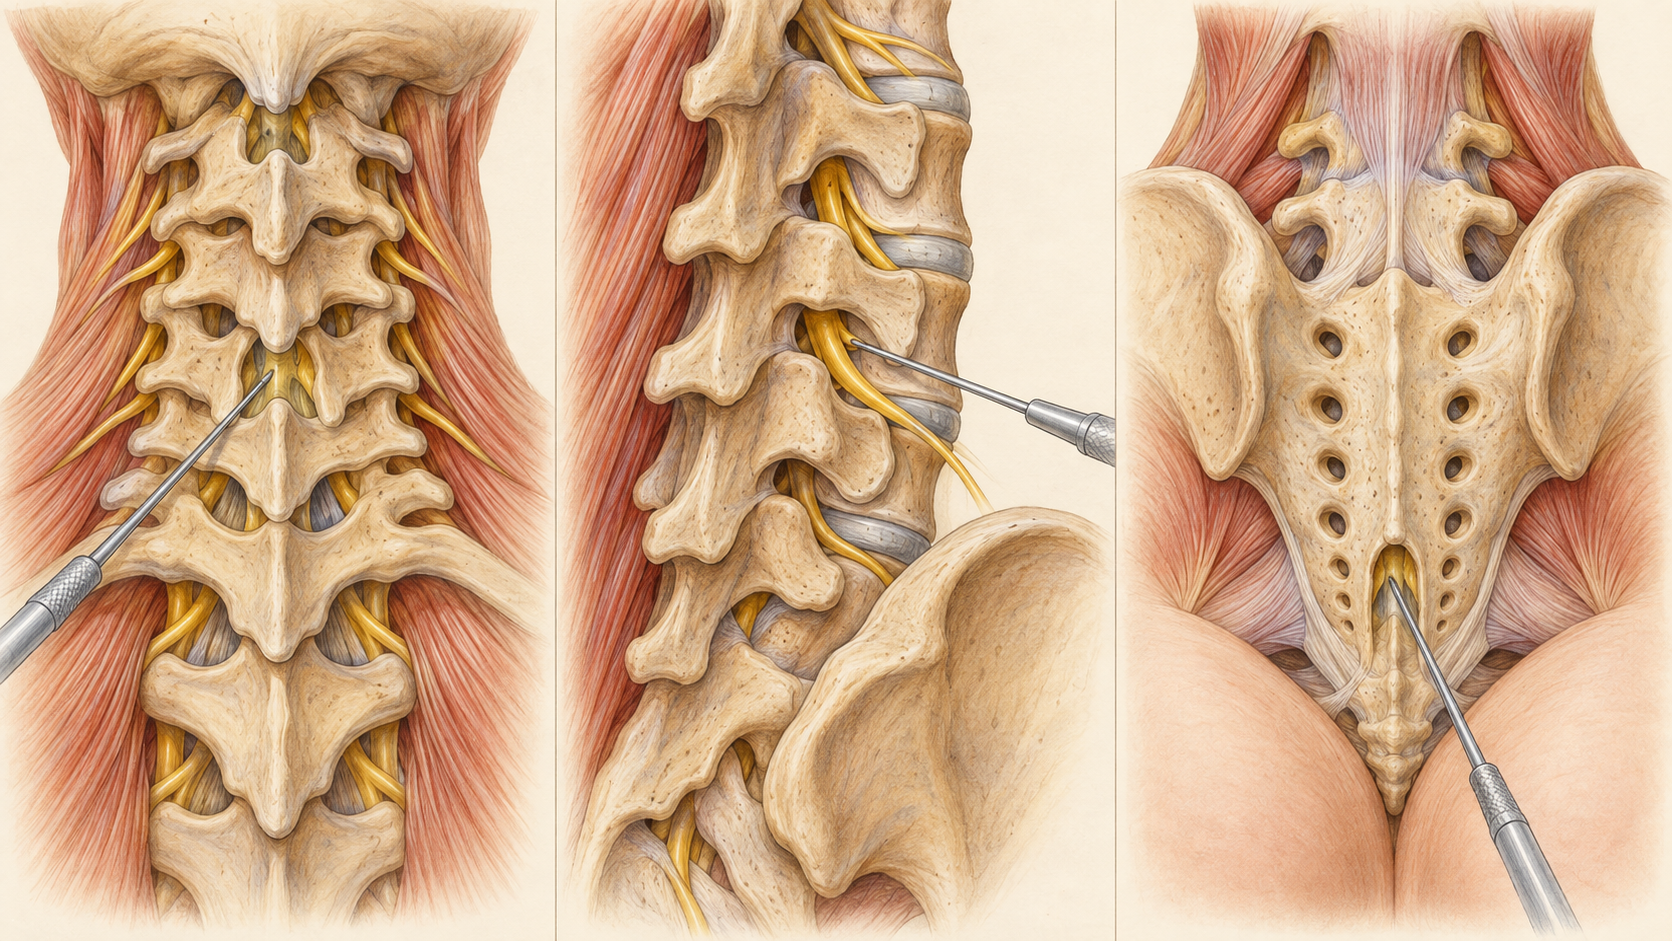
The sacral hiatus is an opening near the lower end of the sacrum. Medication introduced there must travel upward toward the intended lumbosacral region. Anatomy, scarring, volume, and technique can influence distribution, so access route and clinical target are not interchangeable.
Learn what may come next
Related guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Related treatments
Epidural Steroid Injections
Compare the ESI family, general sequence, limitations, and cervical, lumbar, and caudal variants.
Open this guideSpecific treatment
Cervical Epidural Steroid Injection
Cervical ESI anatomy, selection context, procedure considerations, risks, and recovery.
Open this guideSpecific treatment
Lumbar Epidural Steroid Injection
Lumbar ESI anatomy, selection context, procedure considerations, risks, and recovery.
Open this guideRelated care
Conditions this treatment may be considered for
These related guides show educational connections. They do not establish candidacy, a recommendation, or a required sequence.
Alternative
Lumbar Radiculopathy / Sciatica
Alternative epidural access only when anatomy, prior surgery, target, and clinical plan support it.
Explore this pageAlternative
Lumbar Spinal Stenosis
Alternative access pathway when target, anatomy, prior surgery, and symptom pattern support it.
Explore this pageAlternative
Chronic / Low Back Pain
Alternative route for selected lumbar nerve-root leg symptoms, including some patients after spine surgery
Explore this pageAlternative
Spinal Stenosis
Alternative route for selected lumbar stenosis leg symptoms; evidence for lasting improvement is limited
Explore this pagePatient selection
Questions that decide whether a caudal epidural steroid injection fits
Selection begins with a clinically coherent radicular syndrome and a specific anatomic target. It also considers competing diagnoses, prior treatment, medication and bleeding risk, infection risk, goals, and whether a procedure is the right next decision.
A clinically coherent radicular symptom pattern
Imaging or other findings that support the intended anatomic target when imaging is indicated
Persistent functional limitation despite appropriate initial care or a time-sensitive reason for a procedure discussion
A risk review that supports proceeding and a clear plan for reassessment
Evidence at a glance
Evidence at a glance
Study results depend on diagnosis, selection, comparator, technique, outcome, and follow-up.
Caudal access is an approach through the sacral hiatus; anatomy, scarring, volume, and technique can influence medication distribution.
Evidence for caudal epidural injection is heterogeneous and does not establish universal superiority over another route.
Potential benefit depends on the diagnosis and target, and no response mandates a repeat procedure.
Decision process
Steps before a caudal epidural steroid injection
An epidural injection is an optional treatment discussion, not an automatic step. The response must be reassessed against the usual symptoms and meaningful activities. A limited, absent, or discordant response should reopen the diagnosis and alternatives instead of triggering an automatic series.
Confirm the diagnosis and intended target
Review alternatives, medications, medical risks, and the off-label status of epidural corticosteroid use
Define measurable functional goals and a reassessment plan before proceeding
A staged decision
How a caudal epidural steroid injection works
The clinician confirms the diagnosis and why caudal access is being considered, reviews alternatives and risks, and uses image guidance to verify placement and spread as appropriate. The response is reassessed against predefined symptoms and functional goals; no result mandates repetition.
Decision quality matters
Evidence, limits, and who it may fit
A related listing or scan finding does not establish candidacy. Evidence and uncertainty must be matched to the individual question.
Risks and limits
Caudal epidural steroid injection risks and limits
Caudal access is an approach through the sacral hiatus; anatomy, scarring, volume, and technique can influence medication distribution. Evidence for caudal epidural injection is heterogeneous and does not establish universal superiority over another route. Potential benefit depends on the diagnosis and target, and no response mandates a repeat procedure.
An injection does not repair a disc, reverse stenosis, or guarantee that surgery can be avoided.
Bleeding, infection, allergic or medication effects, transient symptom change, and rare serious neurologic injury require individualized consent.
Route, medication, frequency, sedation, medication holds, and aftercare are clinician decisions and are not universal protocols.
The visit
Your consultation for a caudal epidural steroid injection
The visit should define the diagnosis, intended target, evidence, alternatives, off-label medication use, risks, and the next useful decision. Route, medication, frequency, sedation, medication holds, and aftercare remain individualized clinician decisions.
Common questions
Caudal Epidural Steroid Injection FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Why choose a caudal route?
It may be considered when the lower access path, target, anatomy, or prior surgery makes it a reasonable option.
Does caudal mean the medication reaches every painful level?
No. Spread varies, and the route must still match a specific clinical plan.
Is caudal injection proven better than other routes?
No. Evidence is heterogeneous and does not establish universal superiority.
Question before procedure
Ask about a caudal epidural steroid injection in Allen, TX
A consultation can clarify whether an epidural injection, another treatment, continued conservative care, or referral fits the clinical picture.
