
Pain location alone does not establish the diagnosis.
Head, face and headache conditions
Supraorbital Neuralgia
Supraorbital Neuralgia describes pain suspected to arise from the supraorbital nerve. The pattern may include localized tenderness or sensory symptoms, but overlapping headache, facial, dental, joint, cervical, and other disorders must remain in the differential.
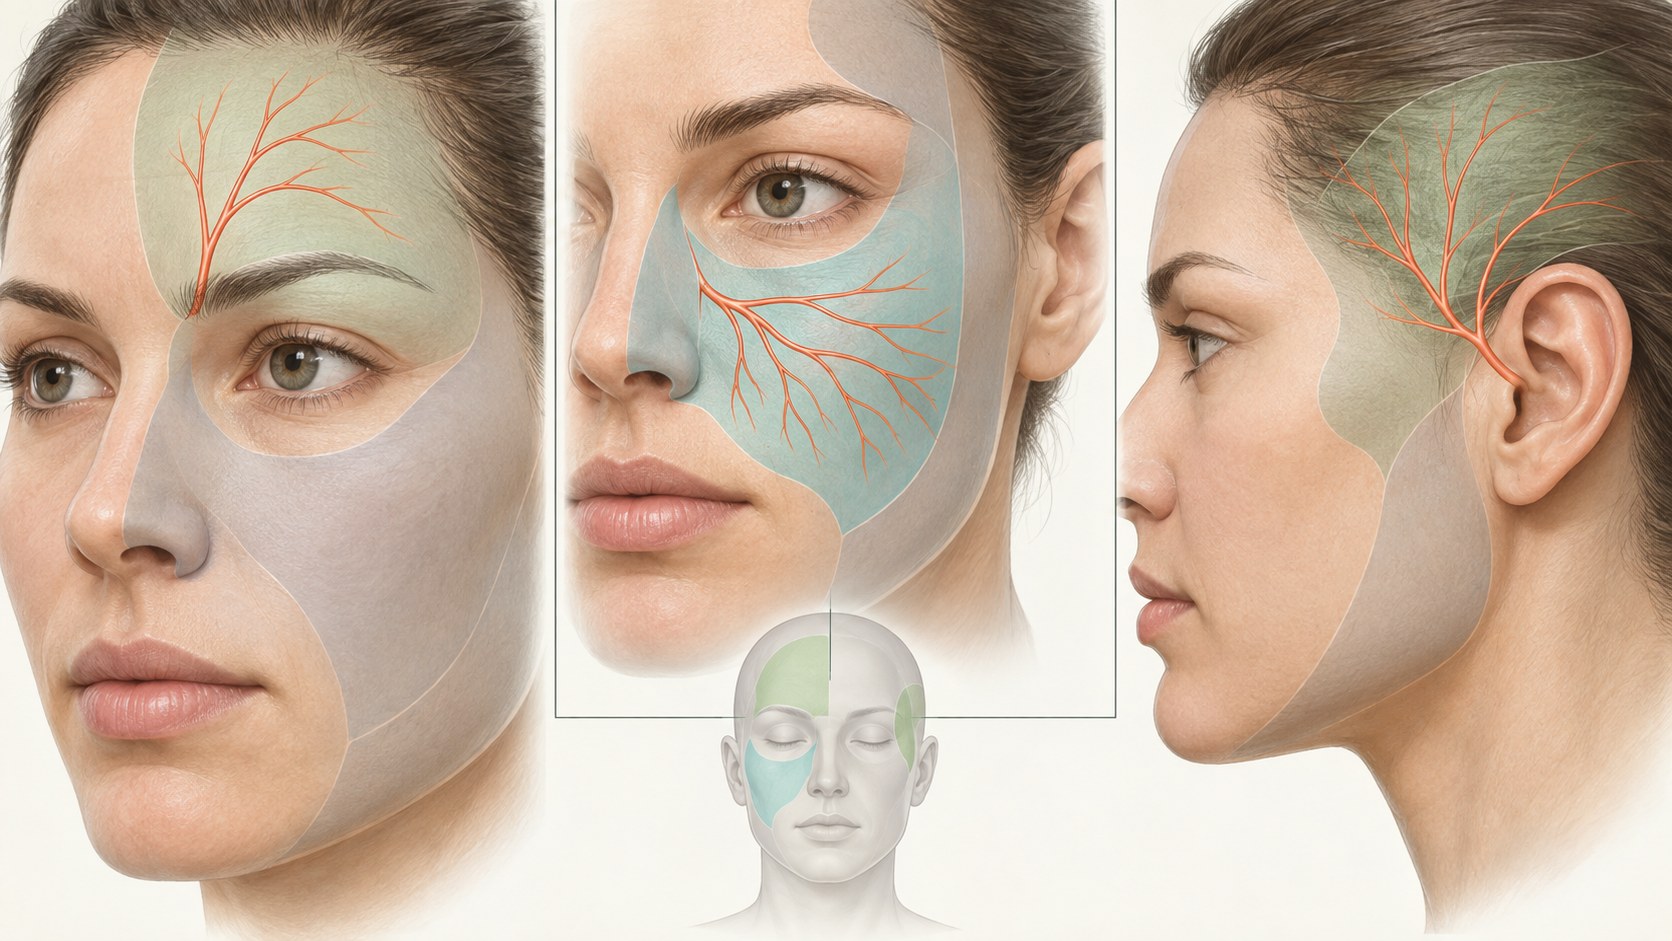
Quick orientation
What to know first
Primary headache, cranial neuralgia, cervical referral, eye, sinus, dental, vascular, and other causes can overlap.
Red flags and a changing neurologic pattern can change the timing and destination of care.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
Supraorbital Nerve Block
May contribute to a diagnostic pathway when supraorbital neuralgia is clinically suspected.
May come later
A later procedure is considered only when evaluation and the response to earlier steps support it.
Later treatment option
Supraorbital Radiofrequency Treatment
May be considered only within a reviewed sequence after diagnosis and response to diagnostic block; evidence and patient-selection review remain required.
Choose the guide that matches your question
Explore the specific guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Care overview
Headache Disorders
Orientation for patients researching recurrent or persistent headache patterns and the practice's evaluation/referral boundaries.
Open this guideClinical guide
Auriculotemporal Neuralgia
Auriculotemporal-distribution facial or temporal pain, diagnostic differentiation, and appropriately selected treatment pathways.
Open this guideClinical guide
Infraorbital Neuralgia
Infraorbital-distribution facial pain, diagnostic differentiation, and appropriately selected treatment pathways.
Open this guideSymptoms are clues, not a diagnosis
What supraorbital neuralgia can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
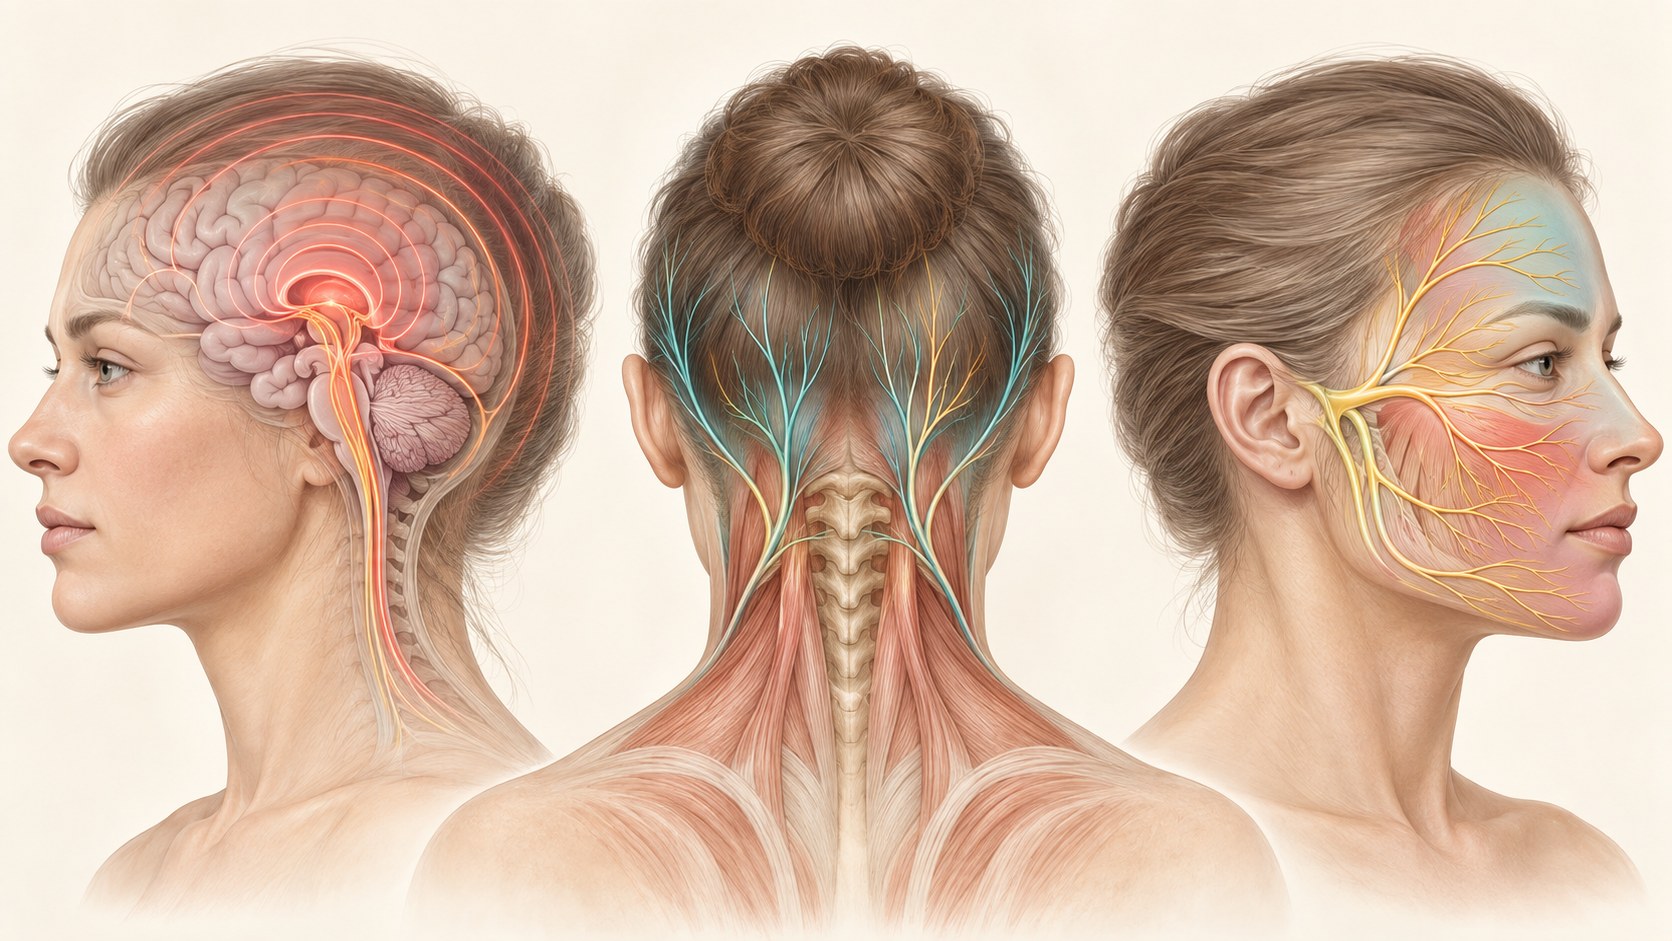
Timing, attack duration, quality, triggers, sensory changes, nausea, light sensitivity, autonomic features, and tenderness help define the pattern.
A named superficial nerve territory can be relevant, but neighboring branches and primary headache disorders may overlap.
Function, sleep, medication use, trauma, infection, systemic disease, and progression shape the evaluation.
Relevant anatomy
What causes supraorbital neuralgia
The supraorbital nerve supplies sensation in the forehead and anterior scalp above the orbit. Its territory overlaps nearby sensory branches and sits near structures that can create referred pain, so a map of symptoms or one tender point is not diagnostic.
History and examination first
How supraorbital neuralgia is diagnosed
Evaluation begins with classification of the headache or neuralgia pattern, a focused neurologic and craniofacial examination, review of red flags, and selective testing or referral. A tender point or temporary block response can add information but does not independently prove the diagnosis.
Keep the differential open
Conditions that can feel like supraorbital neuralgia
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Migraine, frontal sinus, orbital, or eye disorder
Supratrochlear neuralgia, post-traumatic neuropathy, or another trigeminal pain syndrome
Primary headache or a secondary neurologic, ophthalmic, dental, ENT, vascular, infectious, inflammatory, or traumatic cause
Core care
Non-surgical care for supraorbital neuralgia
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Diagnosis-specific education and a headache or symptom diary when useful
Medication and overuse review with the appropriate clinician
Physical or behavioral strategies matched to the diagnosis and functional goals
Reassessment when pattern, neurologic findings, frequency, or treatment response changes
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Clinical descriptions emphasize pain in the supraorbital territory, local tenderness, and diagnostic uncertainty.
Published radiofrequency studies are small and largely retrospective.
Pulsed and thermal radiofrequency use different mechanisms and risk profiles.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When supraorbital neuralgia needs urgent care
These findings can change the timing or destination of care.
A sudden severe headache that reaches maximum intensity rapidly
New weakness, confusion, fainting, seizure, fever with neck stiffness, or new vision loss
Headache after major trauma, during pregnancy or postpartum, with cancer or immune suppression, or with a rapidly changing pattern
The visit
Your first visit for supraorbital neuralgia
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the exact pain pattern, timing, associated symptoms, triggers, and functional effect
Perform a neurologic, head and neck, cranial nerve, musculoskeletal, and sensory examination as appropriate
Use imaging, laboratory testing, ophthalmic, dental, ENT, or neurologic referral selectively
Choose education, medical management, rehabilitation, a target-specific procedure discussion, or referral without assuming a fixed sequence
Common questions
Supraorbital Neuralgia FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Does pain in the area associated with Supraorbital Neuralgia prove neuralgia?
No. A sensory territory can overlap other headache, facial, dental, joint, cervical, and referred pain sources.
Can a helpful nerve block confirm Supraorbital Neuralgia?
No. A temporary response may add information, but it is interpreted with the full clinical pattern and alternatives.
Is radiofrequency an automatic next step for Supraorbital Neuralgia?
No. Evidence, diagnosis, target confidence, risks, alternatives, and goals require a separate review.
Diagnosis before procedure
See a pain specialist for supraorbital neuralgia in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
