
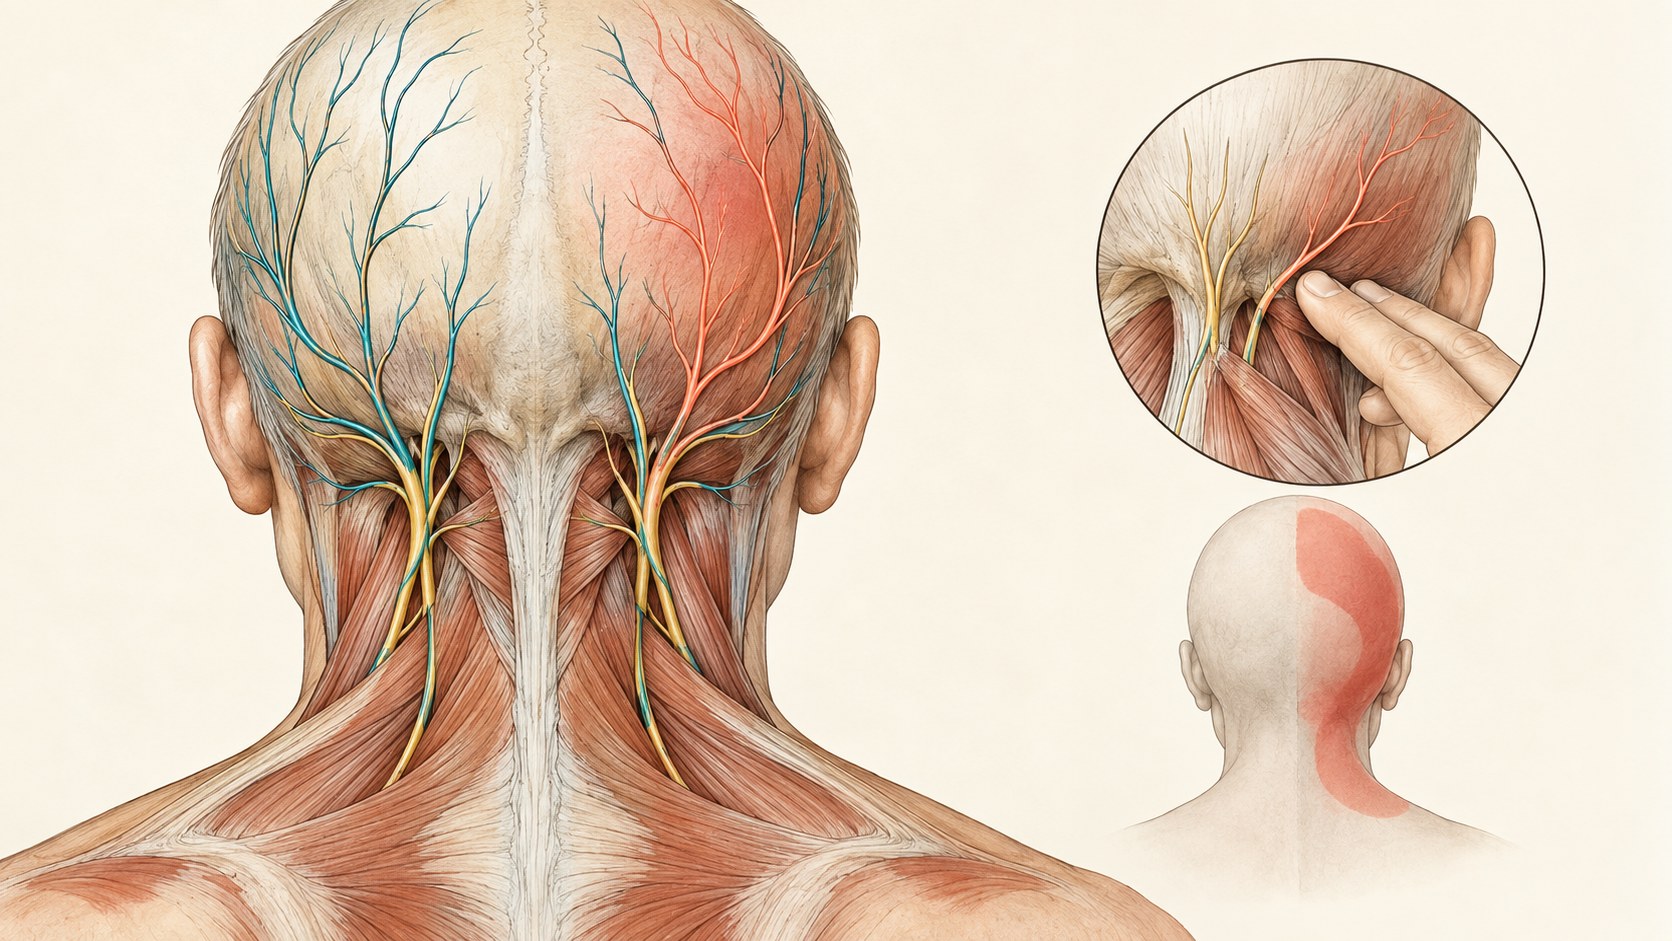
The pain follows an occipital nerve distribution and is often paroxysmal.
Head & Headache
Occipital Neuralgia
Occipital neuralgia causes brief or repeated shooting pain in the distribution of the greater, lesser, or third occipital nerves, often with tenderness or altered sensation. Similar pain can come from migraine or upper-cervical structures, so the label requires more than pain at the back of the head.
Quick orientation
What to know first
Tenderness and temporary block response can support the diagnosis but are not interpreted alone.
PNS may enter selected discussions but is not presented as a preferred treatment.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
Occipital Nerve Block
Target-specific block may contribute to diagnosis and short-term therapeutic assessment.
May come later
A later procedure is considered only when evaluation and the response to earlier steps support it.
Later treatment option
Occipital Radiofrequency Treatment
Later therapeutic step only after target confirmation and appropriate response assessment.
Alternatives, not a sequence
These options may be considered separately; one does not automatically lead to another.
Selected alternative
Peripheral Nerve Stimulation
Potential alternative for selected refractory named peripheral-nerve pain after diagnosis-specific review.
Symptoms are clues, not a diagnosis
What occipital neuralgia can feel like
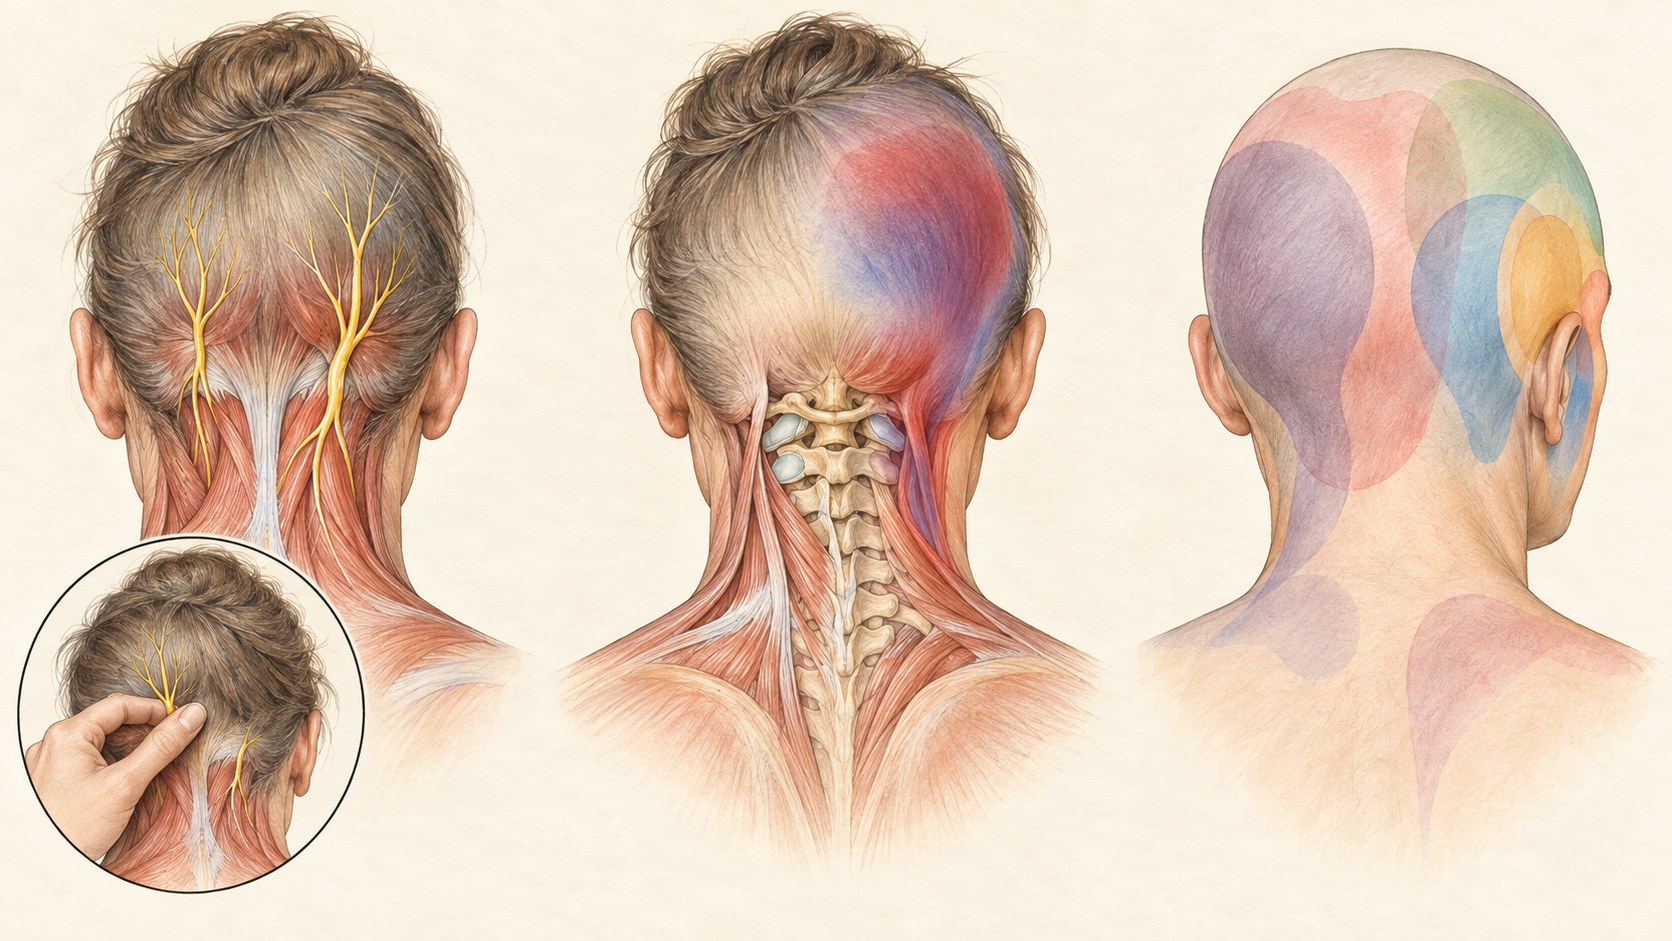
Symptoms help define the pattern but do not confirm the diagnosis by themselves. Distribution, timing, neurologic findings, and important alternatives shape the evaluation.
Shooting, stabbing, or electric pain from the upper neck into the scalp
Tenderness over an occipital nerve
Altered sensation or pain from light touch in the affected scalp
Relevant anatomy
What causes occipital neuralgia
The greater occipital nerve arises primarily from the C2 dorsal ramus and travels through posterior neck tissues to the scalp. The lesser and third occipital nerves supply neighboring territories. Muscles, joints, migraine mechanisms, and other cranial or cervical disorders can produce overlapping pain.
History and examination first
How occipital neuralgia is diagnosed
Evaluation maps the attacks, scalp distribution, triggers, tenderness, sensory findings, neck motion, neurologic status, and headache features. A diagnostic occipital nerve block can support the diagnosis when interpreted with the clinical criteria.
Keep the differential open
Conditions that can feel like occipital neuralgia
A safe diagnosis keeps common and serious alternatives open until the history and examination support a narrower conclusion.
Migraine with occipital pain
Cervicogenic headache from upper-cervical structures
Tension-type headache or myofascial pain
Structural, vascular, infectious, or inflammatory headache causes
Core care
Non-surgical care for occipital neuralgia
Procedure discussions belong inside a broader plan that protects function and addresses the underlying condition.
Address posture, mobility, sleep, and muscle contributors when relevant
Use headache-directed medication or rehabilitation when the diagnosis supports it
Consider an occipital nerve block for diagnostic and short-term therapeutic information
Escalate only after the diagnosis and prior response are clear
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and patient selection affect how a finding should be used.
ICHD-3 defines a characteristic paroxysmal distribution with sensory findings and temporary improvement after local anesthetic block.
Block response is supportive but does not eliminate overlapping headache diagnoses.
Occipital nerve stimulation evidence remains largely lower-level and heterogeneous.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, relevant anatomy, prior care, risk, alternatives, goals, and the evidence for the exact indication must align.
Referral and urgent signs
When occipital neuralgia needs urgent care
These findings can change the timing or destination of care.
A sudden severe new headache
Fever, meningismus, confusion, fainting, or new neurologic deficit
New headache with cancer, immune suppression, pregnancy, or recent major trauma
The visit
Your first visit for occipital neuralgia
The visit should narrow the diagnosis, identify safety or referral needs, review prior care, and choose the next useful decision rather than defaulting to a procedure.
Distinguish paroxysmal nerve pain from broader headache features
Examine the scalp, upper neck, and neurologic system
Use a block or imaging only when it answers a focused diagnostic or treatment question
Common questions
Occipital Neuralgia FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is occipital neuralgia the same as migraine?
No. They can overlap, but migraine has its own features and occipital pain alone does not establish neuralgia.
Does a nerve block prove the diagnosis?
Temporary improvement supports the diagnosis when the full clinical pattern fits, but block response is not interpreted in isolation.
Is PNS a standard next step?
No. Occipital stimulation may be considered in highly selected refractory cases, but the evidence is limited and it is not promoted here as a featured option.
Diagnosis before procedure
See a pain specialist for occipital neuralgia in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that best fits the clinical picture.
