
Symptoms, examination, and imaging must be interpreted together.
Spine and nerve conditions
Herniated Disc
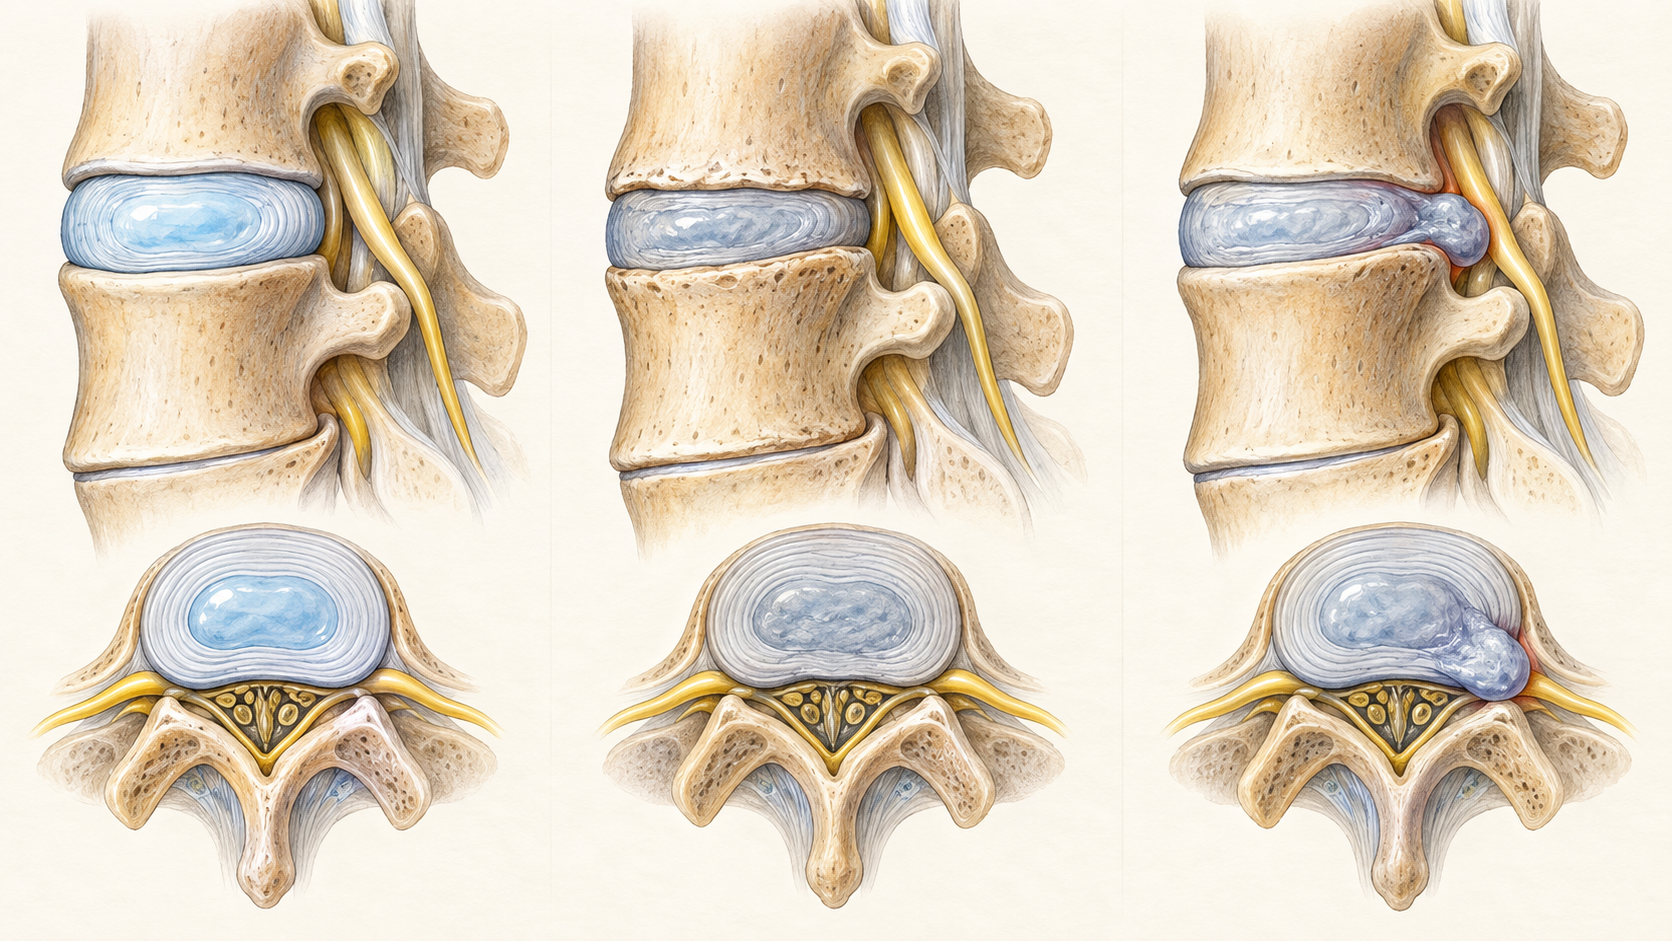
A herniated disc is focal displacement of disc material. It may be incidental, cause local pain, or irritate a nearby nerve root, so the scan and clinical pattern must be interpreted together.
Quick orientation
What to know first
A scan finding can be relevant without being the entire diagnosis.
Progressive neurologic or cord-related findings can change the urgency and destination of care.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Alternatives, not a sequence
These options may be considered separately; one does not automatically lead to another.
Selected alternative
Cervical Epidural Steroid Injection
Region-specific option only when cervical disc pathology and nerve-root symptoms correlate; imaging alone is insufficient.
Selected alternative
Lumbar Epidural Steroid Injection
Region-specific option only when lumbar disc pathology and nerve-root symptoms correlate; imaging alone is insufficient.
Symptoms are clues, not a diagnosis
What herniated disc can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Pain may be only one part of the pattern.
Numbness, tingling, weakness, balance, walking tolerance, and function help define the problem.
Symptoms can overlap with more than one spinal and non-spinal condition.
Relevant anatomy
What causes herniated disc
A disc has a softer center and a fibrous outer ring. Herniation can protrude beyond the usual disc margin and may contact a nerve root. The location, inflammatory response, neurologic findings, and time course help determine its importance.
History and examination first
How herniated disc is diagnosed
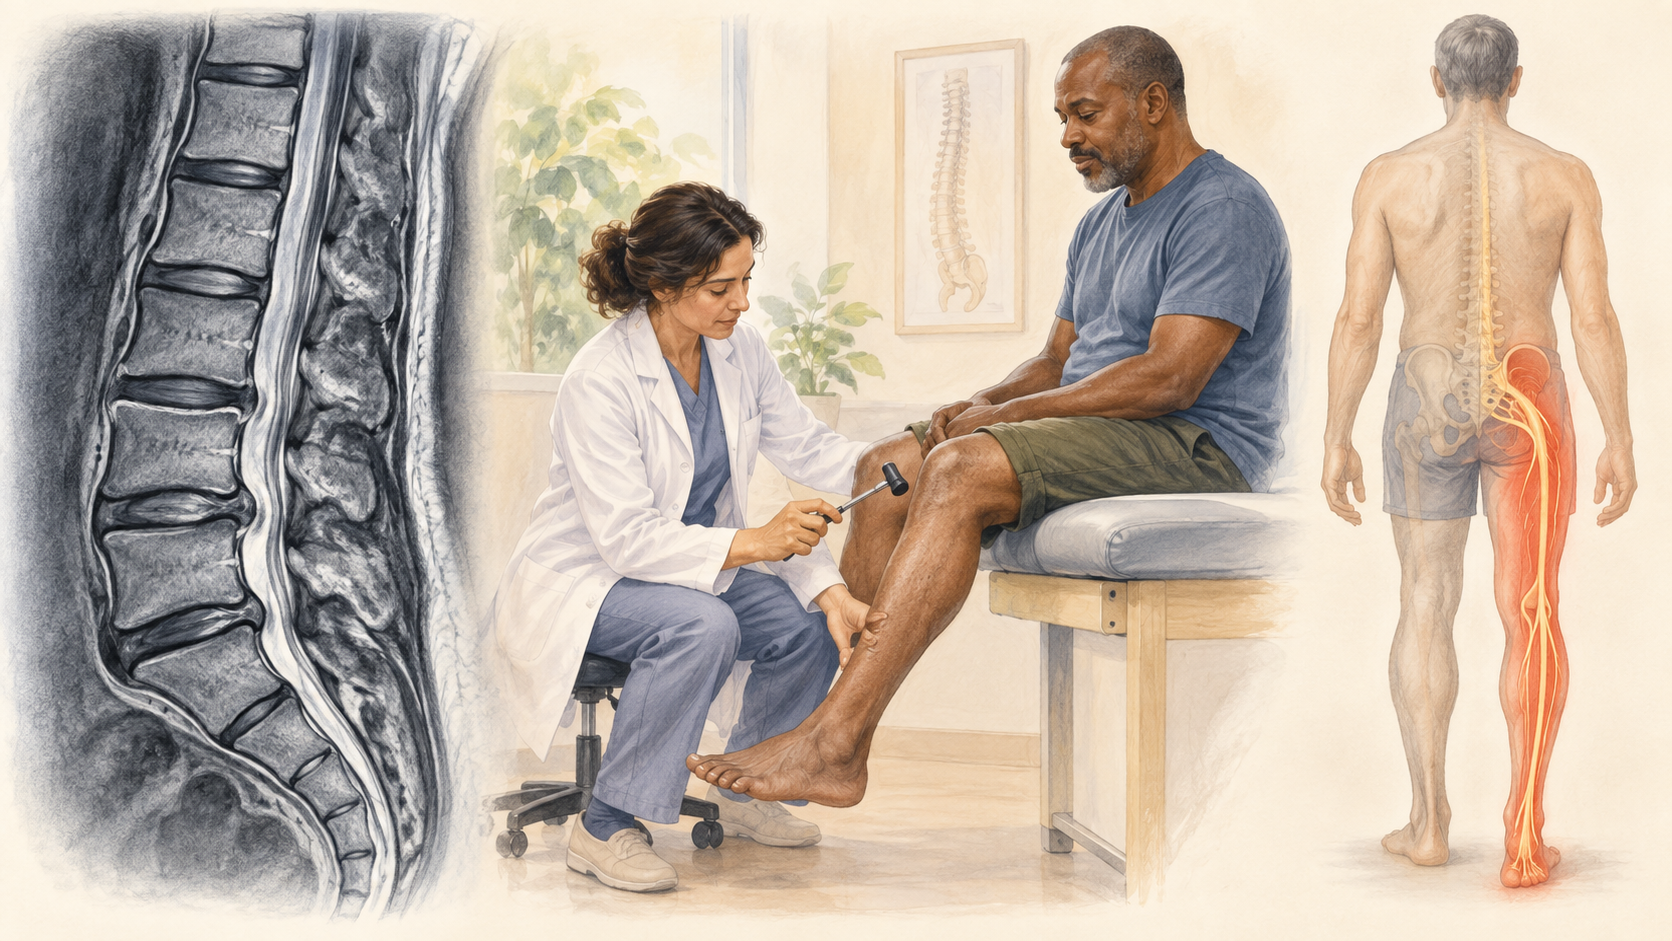
Evaluation begins with the time course, symptom distribution, neurologic examination, functional effects, and urgent features. Imaging can identify anatomy and important alternatives, but the result must correlate with the clinical pattern.
Keep the differential open
Conditions that can feel like herniated disc
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Axial neck or low-back pain without radiculopathy
Peripheral nerve, joint, vascular, or other non-spinal sources
Facet, disc, stenosis, or nerve-root disorders with overlapping features
Infection, fracture, tumor, inflammatory disease, or another urgent cause when the history suggests it
Core care
Non-surgical care for herniated disc
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education and paced movement
Exercise or physical therapy tailored to the diagnosis
Medication review and risk reduction
Reassessment for changing neurologic findings or function
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Disc herniations can be present without symptoms.
Many symptomatic lumbar herniations improve with time, and spontaneous regression can occur.
Epidural injections may offer modest short-term benefit for selected radicular symptoms but do not repair the disc.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When herniated disc needs urgent care
These findings can change the timing or destination of care.
New or progressive weakness
New bowel or bladder dysfunction or saddle numbness
Fever, major trauma, cancer history, or rapidly worsening pain
The visit
Your first visit for herniated disc
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Confirm the symptom pattern and neurologic examination
Review imaging only in the context of symptoms and examination
Choose among rehabilitation, medication, watchful reassessment, procedure discussion, or referral based on the complete picture
Common questions
Herniated Disc FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is a bulging disc the same as a herniated disc?
The terms describe different disc contours, and neither label alone establishes the cause of symptoms.
Can a herniated disc shrink?
Yes. Spontaneous regression is documented, although the course varies and neurologic findings matter.
Does every herniation need surgery?
No. Surgery is considered according to neurologic risk, symptom severity, function, duration, and response to nonoperative care.
Diagnosis before procedure
See a pain specialist for herniated disc in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
