
Peripheral neuropathy, radiculopathy, and focal entrapment are different clinical problems.
Peripheral nerve and neuropathy conditions
Carpal Tunnel Syndrome
Carpal tunnel syndrome is a median nerve entrapment at the wrist. Numbness or tingling in the hand may fit the pattern, but examination and selective testing help separate it from cervical, proximal nerve, joint, and diffuse neuropathy causes.
Quick orientation
What to know first
Symptoms may overlap, so distribution alone does not prove one diagnosis.
Evaluation should look for the cause, neurologic deficits, and conditions that need different care.
What we may consider next
How we may treat this
Treatments that may be considered after an evaluation. Which option, if any, fits depends on the cause of your pain, your examination, prior treatment and your health history; your physician will explain the benefits, limits and risks.
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
Carpal Tunnel Injection
May be considered within a confirmed carpal-tunnel pathway while surgical and other alternatives remain distinct.
Symptoms are clues, not a diagnosis
What carpal tunnel syndrome can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Numbness, tingling, burning, altered sensation, or weakness can occur, but the pattern matters.
Diffuse symptoms in both feet or hands differ from one named-nerve territory or a spinal root pattern.
Function, balance, grip, gait, sleep, and progression help define urgency and next testing.
Relevant anatomy
What causes carpal tunnel syndrome
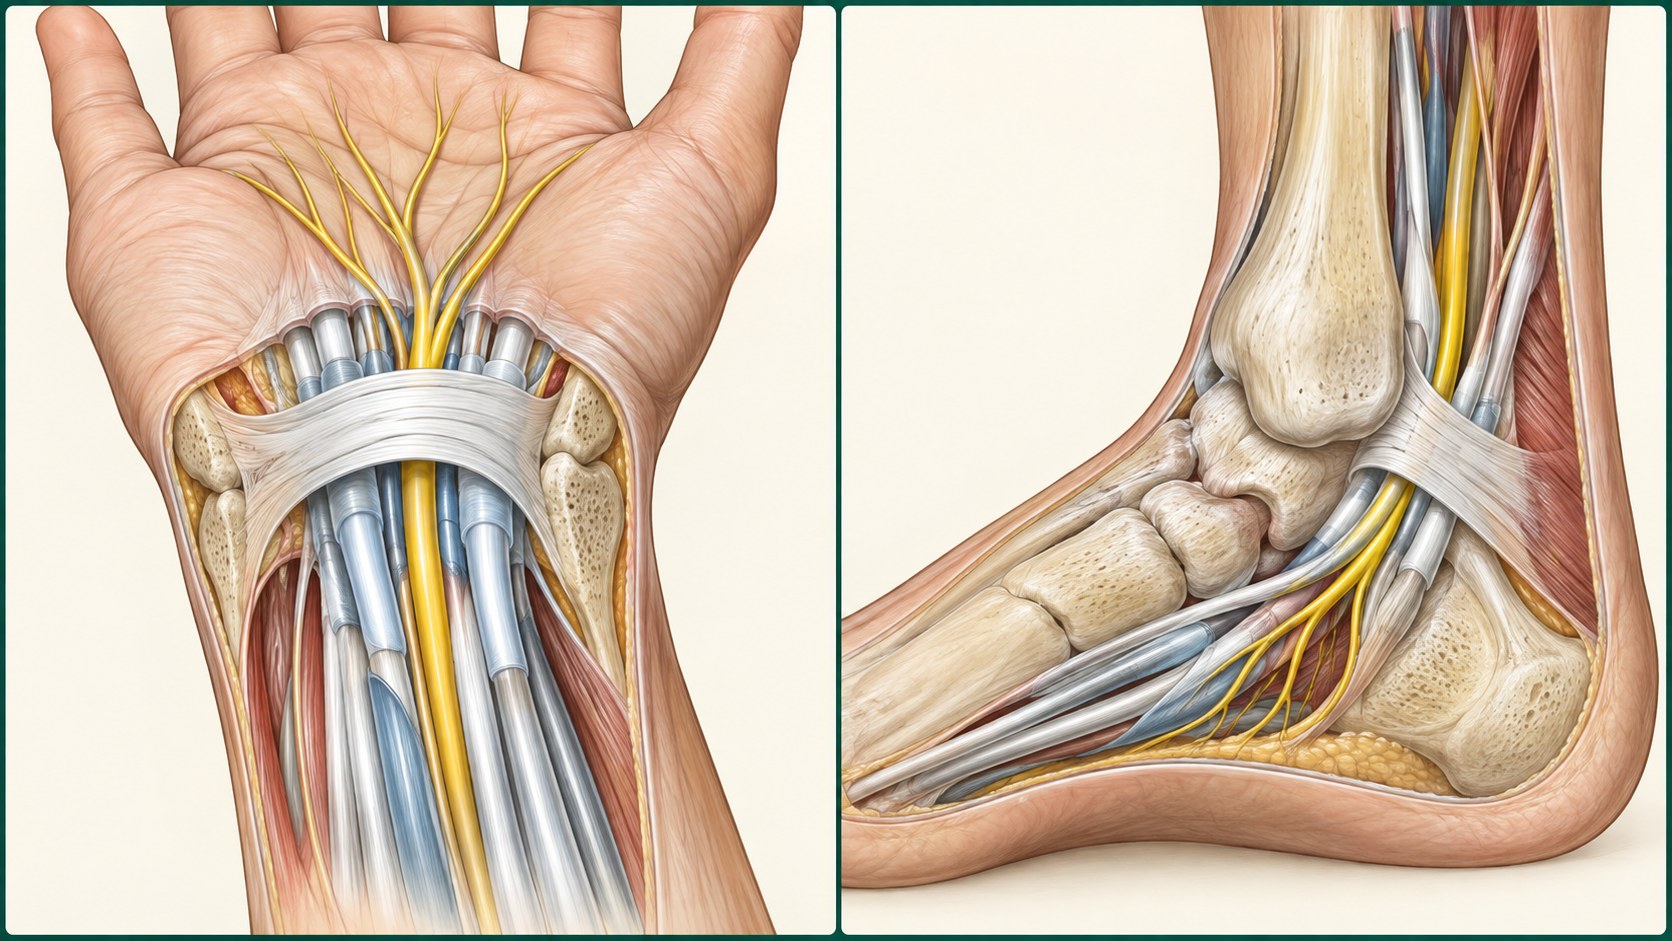
The median nerve and finger-flexor tendons pass beneath the transverse carpal ligament. Symptoms may involve median-innervated digits, but variation and overlap mean that distribution alone is not diagnostic.
History and examination first
How carpal tunnel syndrome is diagnosed
Evaluation combines the history, neurologic and musculoskeletal examination, medical risk review, and selective testing. Electrodiagnostic studies, imaging, ultrasound, or laboratory tests can add information, but no single result replaces clinical correlation.
Keep the differential open
Conditions that can feel like carpal tunnel syndrome
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
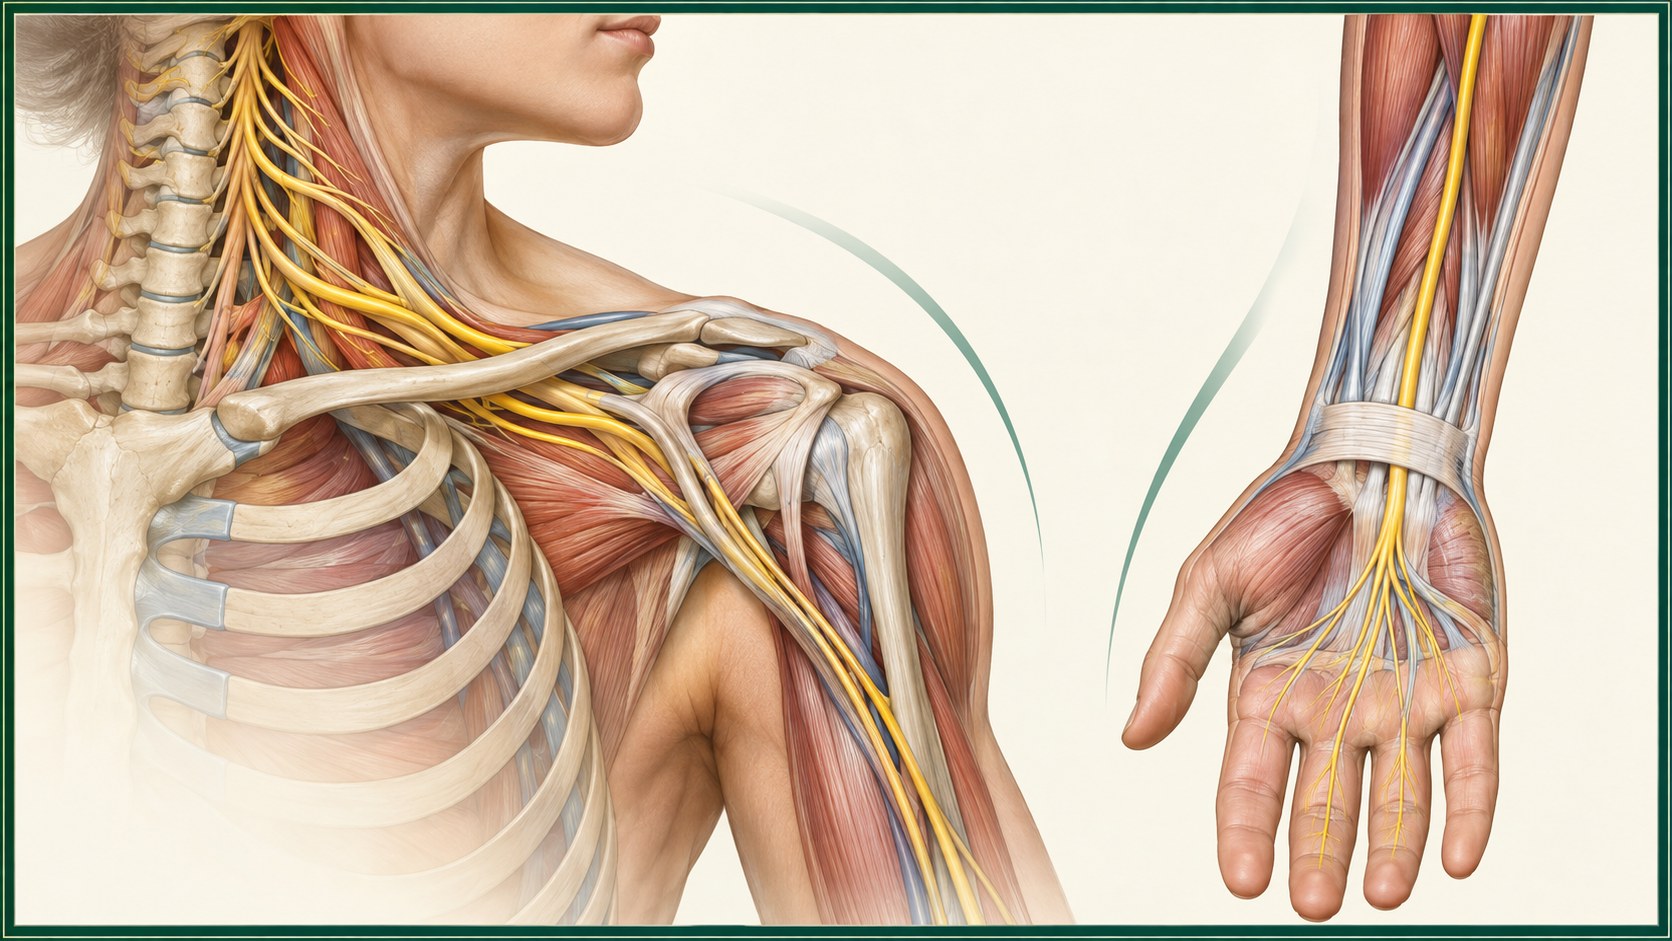
Radiculopathy or spinal cord disease
Focal entrapment versus diffuse polyneuropathy
Joint, tendon, vascular, inflammatory, metabolic, toxic, hereditary, or medication-related causes
Core care
Non-surgical care for carpal tunnel syndrome
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education and protection of vulnerable skin or joints
Activity, therapy, and assistive strategies matched to deficits
Medical evaluation for reversible or treatable contributors
Reassessment when weakness, balance, distribution, or function changes
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Night splinting and corticosteroid injection may provide short-term improvement for selected patients.
The 2024 AAOS guideline concludes that corticosteroid injection does not provide long-term improvement.
Progressive weakness, muscle loss, severe electrodiagnostic findings, or persistent disability can change the referral discussion.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When carpal tunnel syndrome needs urgent care
These findings can change the timing or destination of care.
New or rapidly progressive weakness
Loss of bowel or bladder control or new saddle numbness
Fever, spreading redness, major trauma, or a rapidly changing neurologic pattern
The visit
Your first visit for carpal tunnel syndrome
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the symptom distribution, timing, and functional effect
Examine strength, sensation, reflexes, joints, spine, and named nerve pathways as appropriate
Use imaging, laboratory testing, or electrodiagnostic studies selectively
Choose conservative care, a target-specific procedure discussion, or referral without assuming a fixed sequence
Common questions
Carpal Tunnel Syndrome FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Can neck problems mimic carpal tunnel syndrome?
Yes. Cervical radiculopathy and proximal nerve disorders can overlap with hand symptoms.
Does an injection cure carpal tunnel syndrome?
No. It may provide temporary improvement for selected patients but does not guarantee durable recovery.
When is surgical review considered?
Persistent symptoms, weakness, muscle loss, severe nerve dysfunction, or failure of appropriate nonsurgical care may prompt referral.
Diagnosis before procedure
See a pain specialist for carpal tunnel syndrome in Allen, TX
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
